

Antidepressant augmentation means adding a second medication (often something other than a standard antidepressant) to your current antidepressant to boost a partial response, rather than stopping and switching to a different drug entirely. If you’ve been on an adequate dose of an antidepressant for several weeks and you’re still not feeling like yourself, augmentation is a legitimate, evidence-backed next step for many people, not a sign that something has gone wrong with your treatment.
The options with the strongest research behind them include atypical antipsychotics like aripiprazole, quetiapine, and brexpiprazole, along with lithium, triiodothyronine (T3), and esketamine or ketamine for specific patients. A network meta-analysis of augmentation strategies found benefit across several of these agent classes, though the quality and size of the trials vary quite a bit.
Before your next appointment, bring a written list of every antidepressant you’ve tried, the doses, how long you stayed on each, and what side effects showed up. Your prescriber will likely want baseline labs and vital signs before starting most augmentation agents.
- Augmentation adds a medication to your current antidepressant instead of replacing it.
- Aripiprazole, quetiapine, brexpiprazole, lithium, T3, and (es)ketamine have the most trial support.
- Expect baseline bloodwork or vitals before starting most of these agents.
- Bring your full medication history and response details to your appointment.
Statistic Callout: In a randomized trial in older adults with treatment-resistant depression, augmenting with aripiprazole produced better outcomes than switching to a different antidepressant, reinforcing augmentation as a viable path rather than a last resort.
Key Takeaways
Antidepressant augmentation works best when the agent is matched to your specific symptoms and monitored on a set schedule, with a clear checkpoint around four to six weeks to judge whether to continue or change course.
| Point | Details |
|---|---|
| Augmentation adds, it doesn’t replace | You keep the partial benefit of your current antidepressant while adding a second agent. |
| Aripiprazole has the strongest trial base | Large RCTs and FDA approval as an adjunctive MDD treatment set it apart from other options. |
| Match the agent to your symptoms | Anxious depression, insomnia, and fatigue each point toward different augmentation choices. |
| Monitoring isn’t optional | Lithium, antipsychotics, and T3 each require specific baseline and ongoing lab work. |
| Reassess by week four to six | Limited early improvement is a signal to revisit the plan, not push through unchanged. |
| Imindmental builds monitoring into care | Psychiatry, medication management, and Spravato are offered with proactive lab schedules and telehealth follow-up. |
Table of Contents
- What Is Antidepressant Augmentation and When Does It Apply?
- Which Augmentation Agents Have the Strongest Evidence?
- How Do You Choose the Right Augmentation Strategy?
- What Happens in the First 8 Weeks of Augmentation?
- What Monitoring and Safety Steps Should You Expect?
- What If Augmentation Doesn’t Work?
- How Imindmental Approaches Augmentation and Advanced Care
- What the Research Actually Tells You to Do Next
- Ready to Talk Through Your Options?
- Frequently Asked Questions
- Sources
What Is Antidepressant Augmentation and When Does It Apply?
Antidepressant augmentation is the practice of adding a second agent, often not an antidepressant at all, to a current antidepressant that’s producing only a partial effect. The goal is to build on whatever benefit you’ve already gained rather than starting over. This distinguishes it from switching, which means stopping one antidepressant and beginning another from scratch.
Clinicians typically start thinking about augmentation once you meet criteria for treatment-resistant depression, or TRD. There isn’t one universal definition that every guideline agrees on, but the most common threshold is failure to achieve adequate improvement after one to two antidepressant trials, each given at a sufficient dose for a sufficient length of time (usually at least four to six weeks). Some clinicians consider augmentation after a single failed trial; others wait until two trials from different drug classes haven’t worked. This variation isn’t sloppiness. It reflects genuine disagreement in the field about how much time and how many attempts should pass before a case is labeled resistant.
Why choose augmentation over switching at all? A few practical reasons come up again and again in clinical guidance:
- You keep your partial gains. If an antidepressant has helped even 20 to 30 percent, switching away from it risks losing that progress entirely.
- Augmentation can work faster. You skip the multi-week taper-and-restart cycle that switching often requires.
- You avoid discontinuation symptoms. Stopping an antidepressant abruptly, or even gradually, can trigger withdrawal-like effects that switching amplifies.
- It preserves therapeutic alliance with a medication that’s partially working, which matters more than it sounds when you’ve already been through several trials.
Switching tends to make more sense when you’ve had zero meaningful response to the current antidepressant, when side effects are intolerable, or when you haven’t actually completed an adequate trial yet (wrong dose, too short a duration, or poor adherence). Augmentation assumes there’s something worth building on.
Before adding an agent, most clinicians will run a baseline evaluation that typically includes:
- A review of your full psychiatric and medication history, including past augmentation attempts.
- Basic metabolic labs (glucose, lipids) if an atypical antipsychotic is being considered.
- Thyroid and kidney function tests if lithium or T3 is on the table.
- A cardiovascular history check, particularly for older adults or anyone with heart disease.
- A discussion of pregnancy status and plans, since several augmentation agents carry reproductive risks.
If you’re unsure whether you’ve had an “adequate” trial in the first place, that’s worth raising directly. Reviewing what hasn’t worked yet is often the first real conversation to have before augmentation even enters the picture.
Which Augmentation Agents Have the Strongest Evidence?
Not all augmentation strategies rest on the same quality of evidence, and the differences matter when you’re weighing risk against benefit. Here’s how the major classes stack up.
Atypical antipsychotics: the best-studied option
Aripiprazole has more randomized controlled trial support behind it than almost any other augmentation agent. Two large 14-week, double-blind, placebo-controlled trials found that adding aripiprazole to an antidepressant improved both response and remission rates compared with placebo, evidence solid enough that aripiprazole carries FDA approval specifically as an adjunctive treatment for major depressive disorder. That regulatory approval is unusual among augmentation agents, most of which are used off label.
Quetiapine and brexpiprazole also have randomized trial data supporting their use as adjuncts, though brexpiprazole’s evidence base is somewhat newer and smaller in total trial volume than aripiprazole’s. All three carry real tolerability trade-offs: weight gain, sedation, and metabolic changes including elevated glucose and lipids show up across the class. Akathisia (a restless, can’t-sit-still sensation) is a known issue with aripiprazole specifically, and it’s worth naming to your prescriber early rather than pushing through it.
Lithium: old, cheap, and still effective
Lithium has one of the longest track records of any psychiatric medication, and its use as an antidepressant augmentation strategy predates most of the atypical antipsychotics by decades. The efficacy signal is real, but lithium demands a level of monitoring that newer agents don’t. Blood levels have a narrow therapeutic window, meaning too little does nothing and too much becomes toxic. Lifetime surveillance of kidney and thyroid function is standard because hypothyroidism develops in a meaningful minority of patients on long-term lithium, something clinicians need to anticipate rather than discover after the fact.
T3 (triiodothyronine): a smaller, older signal
Thyroid hormone augmentation, specifically T3 rather than the more commonly prescribed T4, has a meta-analytic signal supporting its use, but the individual trials behind that signal tend to be small. T3 is generally avoided or used cautiously in older adults and in anyone with uncontrolled cardiac disease, since thyroid hormone can accelerate heart rate and increase cardiac workload. It’s a reasonable option to discuss, but it shouldn’t be presented to you as equivalent in evidence weight to aripiprazole.
Antidepressant-to-antidepressant combinations
Sometimes the “augmentation” agent is simply a second antidepressant with a different mechanism. Bupropion is often added for its activating, non-sedating profile, particularly when fatigue or low motivation dominate the symptom picture. Mirtazapine gets added when sleep and appetite are the main problems, since its sedating and appetite-stimulating properties work in the opposite direction of most SSRIs and SNRIs. These combinations typically require less baseline lab work than antipsychotics or lithium, which is one reason they’re often tried early.
(Es)ketamine and ketamine: rapid but resource-intensive
Esketamine (brand name Spravato) and IV ketamine represent a different category entirely: rapid-acting agents administered in a supervised clinical setting rather than taken home. The evidence base here is genuinely strong for speed of effect, with some patients reporting improvement within hours to days rather than weeks. That speed comes with logistical requirements: esketamine is FDA-approved specifically for patients who have already tried at least two antidepressants without adequate benefit, and every dose is administered under direct clinical observation because of dissociative effects and blood pressure changes.
Statistic Callout: A broader meta-analysis spanning 115 trials and 48 different treatment strategies found some of the largest effect sizes for cognitive behavioral therapy, (es)ketamine, and risperidone, while aripiprazole and quetiapine had substantial supporting evidence spread across numerous individual studies.
A note on the evidence itself: head-to-head trials comparing one augmentation agent directly against another are rare. Most of what we know comes from placebo-controlled trials of individual agents, which means decisions between, say, aripiprazole and lithium often come down to practical factors like monitoring burden and your prior tolerability history rather than a clean efficacy comparison. Some industry-funded trials also raise legitimate questions about publication bias, which is part of why guideline bodies weigh multiple independent meta-analyses rather than any single study.
How Do You Choose the Right Augmentation Strategy?
The right augmentation agent isn’t the one with the flashiest trial data. It’s the one that fits your specific symptom pattern, medical history, and tolerance for monitoring. Here’s how clinicians typically approach that decision.
- Match the agent to your dominant symptoms. Anxious or agitated depression often points toward an atypical antipsychotic. Insomnia and poor appetite often make mirtazapine the more logical add. Prominent fatigue and low motivation frequently steer toward bupropion. This kind of symptom-directed selection is increasingly how psychiatrists approach augmentation instead of trial-and-error.
- Rule out contraindications first. Cardiac disease limits T3 and warrants caution with some antipsychotics. Pregnancy changes the calculus for nearly every agent on this list. Kidney disease complicates lithium significantly.
- Review what you’ve already tolerated. If a prior antidepressant caused significant weight gain, another agent from a metabolically risky class may not be your best next step.
- Weigh the monitoring burden honestly. Lithium means regular bloodwork indefinitely. Esketamine means in-clinic visits with observation periods. Bupropion or mirtazapine require far less.
- Factor in your own preference. Two agents with similar evidence but very different monitoring demands aren’t equally good choices for every patient, and your comfort with the process matters clinically, not just logistically.
Pro Tip: Write down three questions before your appointment: What benefit should I realistically expect, and by when? What does the monitoring schedule actually look like month to month? And if side effects show up, what’s the plan, dose adjustment, a different agent, or stopping altogether? Walking in with these ready saves a lot of back-and-forth.
What Happens in the First 8 Weeks of Augmentation?
Starting an augmentation agent is a process, not a single decision made in one appointment. Knowing what to expect at each stage helps you and your prescriber judge whether it’s working.
- Pre-start checklist. Expect baseline labs specific to the agent chosen (metabolic panel for antipsychotics, kidney and thyroid function for lithium or T3), a medication reconciliation to check for interactions, and informed consent covering expected benefits and risks.
- Starting dose. Doses for augmentation are typically much lower than doses used to treat psychosis or bipolar disorder. Aripiprazole augmentation, for example, often starts around 2 to 5 milligrams daily and gets titrated based on response and tolerability. These figures are illustrative only. Your actual starting dose should come from your prescriber based on your history.
- Weeks 1 to 2: watch for side effects, not results. Early on, you’re more likely to notice side effects (restlessness, sedation, gastrointestinal changes) than mood improvement. That’s expected and doesn’t mean the medication has failed.
- Weeks 4 to 6: the first real checkpoint. Most clinical trials assess whether an augmentation strategy is working somewhere in the 6 to 12 week range, but an earlier signal often shows up by week four. Less than roughly 30 percent improvement in symptoms by that point suggests a lower likelihood of eventual full response, which is a common trigger for reassessing the plan rather than waiting it out indefinitely.
- Weeks 6 to 12: continuation or change. If you’re seeing solid improvement, your prescriber will likely continue and reassess dosing. If not, this is typically when a switch to a different augmentation strategy, or a different approach entirely, gets discussed.
- Follow-up visits. Expect more frequent check-ins early on (every two to four weeks isn’t unusual) tapering to monthly or longer once you’re stable. Consistent medication management during this window is often what separates a successful augmentation trial from one that gets abandoned too early or continued too long.
What Monitoring and Safety Steps Should You Expect?
Every augmentation agent worth considering also comes with a monitoring obligation, and skipping it isn’t a shortcut, it’s a risk.
For atypical antipsychotics (aripiprazole, quetiapine, brexpiprazole), expect baseline weight and BMI, fasting glucose or HbA1c, and a lipid panel, with periodic rechecks because metabolic changes like weight gain and glycemic shifts often begin within weeks of starting, not months.
For lithium, baseline kidney and thyroid function tests come first, followed by a serum lithium level once you’ve reached steady state (usually five to seven days after a dose change), then periodic rechecks indefinitely. Common adverse effects include tremor, increased thirst and urination, and long-term thyroid changes.
For T3, cardiac caution is the headline: avoid it in uncontrolled cardiac disease, and expect periodic thyroid function monitoring alongside attention to heart rate and rhythm.
For esketamine or ketamine, every dose happens in a supervised clinical setting with blood pressure monitoring before, during, and after administration, plus observation for dissociation and cognitive changes before you’re cleared to leave.
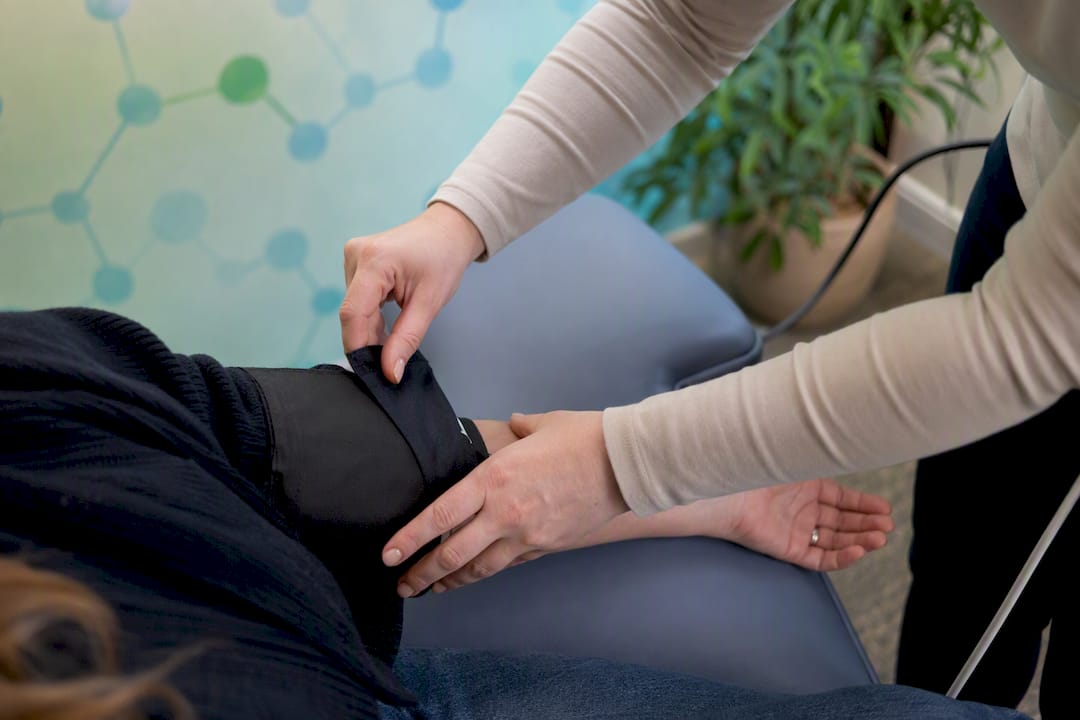
Statistic Callout: Systematic reviews of augmentation strategies consistently flag these monitoring protocols as essential to safe use, not optional add-ons, precisely because several of these agents carry adverse effect profiles that develop silently without regular labs.
Know the signs that warrant urgent contact with your care team regardless of which agent you’re on: a sudden increase in suicidal thoughts, severe neurological symptoms like confusion or uncontrolled movements, chest pain, or significant blood pressure changes. These aren’t “wait for the next appointment” situations.
What If Augmentation Doesn’t Work?
If one or two augmentation attempts haven’t moved the needle, you still have real options, and none of them mean you’ve run out of road.
- Transcranial magnetic stimulation (TMS) uses magnetic pulses to stimulate targeted brain regions and has solid efficacy evidence for patients who haven’t responded to medication trials. A typical course runs daily sessions over four to six weeks, and comparing TMS against other neuromodulation options is a reasonable next conversation if medication augmentation has stalled.
- Electroconvulsive therapy (ECT) remains the most effective option for severe, refractory depression, particularly when safety is urgent (active suicidality, catatonia, or an inability to eat or care for oneself). Recovery involves some short-term memory effects that your care team will walk you through.
- Clinic-based (es)ketamine can also serve as an escalation point beyond oral augmentation agents, given its rapid-acting profile.
- Psychotherapy, especially CBT, shows meaningful effect sizes when combined with medication rather than used as a replacement, and it’s worth keeping in the mix at every stage, not just after pharmacology fails.
A referral to a specialist in treatment-resistant depression makes sense once you’ve tried two or more adequate augmentation strategies without meaningful benefit.
How Imindmental Approaches Augmentation and Advanced Care
I’ve seen how much relief people feel just from understanding that their case isn’t unusual. Treatment resistance is common, and augmentation is a well-established, collaborative next step, not an admission that something failed.
At iMind Mental Health Solutions, augmentation decisions happen through ongoing psychiatry and medication management, where your prior response history and side effect tolerance actually shape the plan instead of a one-size approach. For patients who’ve already tried multiple antidepressants, we also offer Spravato treatment and TMS as guideline-supported next steps beyond oral augmentation.
- Baseline evaluations and labs are built into intake before any new agent starts.
- Telehealth appointments are available for medication management follow-ups across our Florida locations.
- Monitoring schedules are set proactively, not reactively, based on the agent chosen.
This article is educational. Your specific situation, medications, and medical history require an individualized conversation with a licensed prescriber.
What the Research Actually Tells You to Do Next
The honest takeaway from the augmentation literature is that the field knows a lot about what works in isolation and very little about what works best compared to what else. That gap gets glossed over constantly. Patients are often told “we’ll add X” as though X were selected from a ranked list, when in reality the choice usually comes down to your symptom profile, your tolerance for lab draws, and what your prescriber has seen work in similar cases.
Where conventional advice falls short is in treating augmentation as a single decision point rather than a structured trial with a built-in exit ramp. Too many people stay on an augmentation agent for months past the point where the four-week checkpoint should have prompted a change. The agents themselves, aripiprazole, lithium, T3, (es)ketamine, all have real evidence behind them. What’s missing more often is the discipline to reassess on schedule.
If you take one thing from this, prioritize the timeline conversation before you prioritize the drug name. Ask your prescriber when you’ll know if it’s working, not just what you’re taking.
Ready to Talk Through Your Options?
If you’ve read this far because your current antidepressant isn’t cutting it, the next move doesn’t have to be another round of guesswork. Imindmental exists specifically for this stage of care: psychiatric providers who build augmentation plans around your actual history rather than a generic protocol, with the monitoring and follow-up structure built in from day one.
Whether the right next step is starting a low-dose atypical antipsychotic, discussing lithium or T3 with proper lab support, or moving toward a clinic-based option like Spravato when oral strategies haven’t worked, you can get that assessment through telehealth or in person across our Port St. Lucie, Vero Beach, and Stuart locations. For patients also managing sleep, appetite, or medication logistics questions, resources like AM Rx can complement the medication side of your care.
Book a psychiatric evaluation through Imindmental’s psychiatry services to start building an augmentation plan that’s actually tailored to your treatment history.
Frequently Asked Questions
What is the difference between antidepressant augmentation and combination therapy?
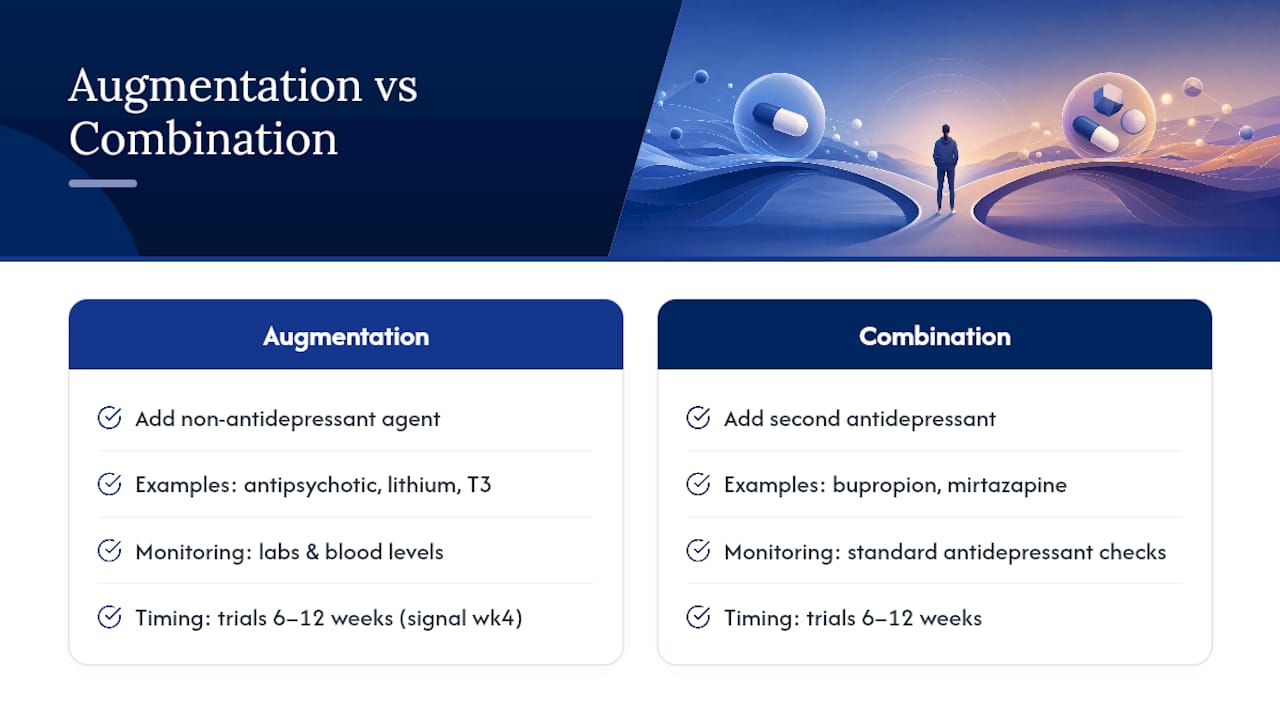
Augmentation typically means adding a non-antidepressant agent, such as an atypical antipsychotic, lithium, or T3, to boost an existing antidepressant’s effect. Combination therapy usually refers to adding a second antidepressant, like bupropion or mirtazapine, alongside the first. The terms overlap in practice, but the distinction matters when discussing monitoring needs.
How long does it take for antidepressant augmentation to work?
Most clinical trials evaluate augmentation outcomes at 6 to 12 weeks, though an early signal often appears by week four, with lower improvement often triggering plan reassessment.
Is lithium augmentation safe for depression?
Lithium has a long track record of effectiveness as an augmentation strategy, but it requires ongoing monitoring of kidney and thyroid function along with periodic blood level checks. It’s generally avoided in people with significant kidney disease and used cautiously during pregnancy.
Can esketamine or ketamine be used instead of oral augmentation agents?
Esketamine (Spravato) is FDA-approved for patients who’ve already tried at least two antidepressants without adequate benefit, making it a later-stage option rather than a first-line augmentation choice. It requires supervised administration in a clinical setting due to its dissociative effects and blood pressure changes.
What should I ask my doctor before starting an augmentation medication?
Ask what improvement to realistically expect and by when, what labs or monitoring the specific agent requires, and what the plan is if side effects appear. Clarifying the timeline for reassessment upfront helps you avoid staying on an ineffective strategy longer than necessary.
Does insurance typically cover antidepressant augmentation treatment?
Coverage varies by plan and by which agent is prescribed, since generic options like lithium or aripiprazole are usually more affordable than newer treatments like esketamine. Checking your specific benefits with your provider or your prescriber’s office before starting is the most reliable way to know your costs.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Augmentation strategies for treatment resistant major depression: A systematic review and network meta-analysis
- Antidepressant Augmentation versus Switch in Treatment-Resistant Geriatric Depression
- Treatment-resistant depression – Mayo Clinic

