

Brain mapping for ADHD cannot diagnose the condition on its own, but it offers something equally valuable: a window into how your brain is actually functioning, which can guide more personalized treatment decisions. Quantitative EEG, or qEEG, is the clinical term for what most people call brain mapping. It measures electrical activity across the scalp, compares your patterns against a normative database, and produces a detailed map of brainwave frequencies. The CDC confirms that ADHD is diagnosed clinically through history, rating scales, and behavioral assessment, not by any single lab test or biomarker. The American Academy of Neurology goes further, cautioning that qEEG should not be used alone to diagnose ADHD because of limited diagnostic specificity and the real risk of false positives.
What qEEG reliably does is different, and arguably more useful for many patients:
- It identifies specific brainwave patterns associated with ADHD subtypes, such as elevated theta or reduced beta activity.
- It helps clinicians distinguish between cortical hypoarousal, delayed maturation, and hyperarousal profiles, each of which responds differently to treatment.
- It guides neurofeedback protocol selection so training targets the right frequency bands for your particular profile.
- It provides a measurable baseline, allowing clinicians to track whether treatment is producing real neurological change over time.
Who should consider requesting a qEEG? If you have treatment-resistant ADHD symptoms, a complex diagnostic picture with comorbid anxiety or mood issues, or you are exploring neurofeedback as part of your care plan, a qEEG assessment adds meaningful clinical information. Ask for it through a board-certified neuropsychologist, psychiatrist, or neurologist who has specific training in qEEG interpretation.
Key Takeaways
qEEG is a clinically valuable adjunct for ADHD subtyping and treatment planning, but it cannot diagnose ADHD on its own and should always be interpreted within a full clinical evaluation.
| Point | Details |
|---|---|
| qEEG is adjunctive, not diagnostic | The AAN and CDC both confirm ADHD diagnosis requires clinical history and rating scales, not a brain scan alone. |
| Elevated theta and reduced beta are the most replicated ADHD markers | These patterns, especially the theta/beta ratio at Cz, guide neurofeedback protocol selection but must be interpreted as part of a full spectral profile. |
| Subtyping drives treatment precision | Hypoarousal, delayed maturation, and hyperarousal profiles each map to different neurofeedback protocols with different clinical targets. |
| Placebo effects and protocol variability are real limits | Some literature report notable short-term improvement in control conditions; standardization across the field remains inconsistent. |
| Imindmental integrates qEEG into coordinated care | Brain mapping at Imindmental is paired with psychiatry, neurofeedback, and TMS, with follow-up recordings to track neurological change. |
Table of Contents
- What is brain mapping (qEEG) and how does it work?
- Which qEEG patterns are most commonly associated with ADHD?
- What does the research say about qEEG and neurofeedback for ADHD?
- How clinicians use qEEG to guide treatment choices
- What to expect from a qEEG appointment
- How qEEG reports are interpreted and who should read them
- When is qEEG most useful, and what should you ask before ordering one?
- How Imindmental uses brain mapping in clinical practice
- Realistic expectations matter as much as the technology
- Brain mapping for ADHD: what Imindmental offers you
- Sources
What is brain mapping (qEEG) and how does it work?
Quantitative EEG differs from a standard clinical EEG in one important way: instead of a neurologist scanning the raw waveform for seizure activity or gross abnormalities, qEEG software transforms that raw signal into statistical maps. Your brainwave data is compared against a normative reference database of age-matched individuals without neurological conditions. The result is a color-coded topographic map showing where your brain’s electrical activity falls above or below expected ranges.
How the recording is collected
A trained EEG technologist places a cap or individual electrodes at standardized scalp positions, typically following the 10–20 international montage system, which uses 19–21 recording sites. Conductive gel reduces impedance at each electrode. Most clinical qEEG sessions include:
- A resting eyes-closed recording (usually 5–10 minutes) to capture baseline activity.
- A resting eyes-open recording to assess how the brain modulates attention-related rhythms.
- Optional task recordings (reading, arithmetic, or continuous performance tasks) that reveal how activity shifts under cognitive load.
The total recording time typically runs 20–40 minutes, not counting setup. The raw data is then processed through artifact rejection (removing eye blinks and muscle noise), and the cleaned signal is analyzed for absolute power, relative power, coherence, and peak frequency in each band.
Frequency bands and what they mean
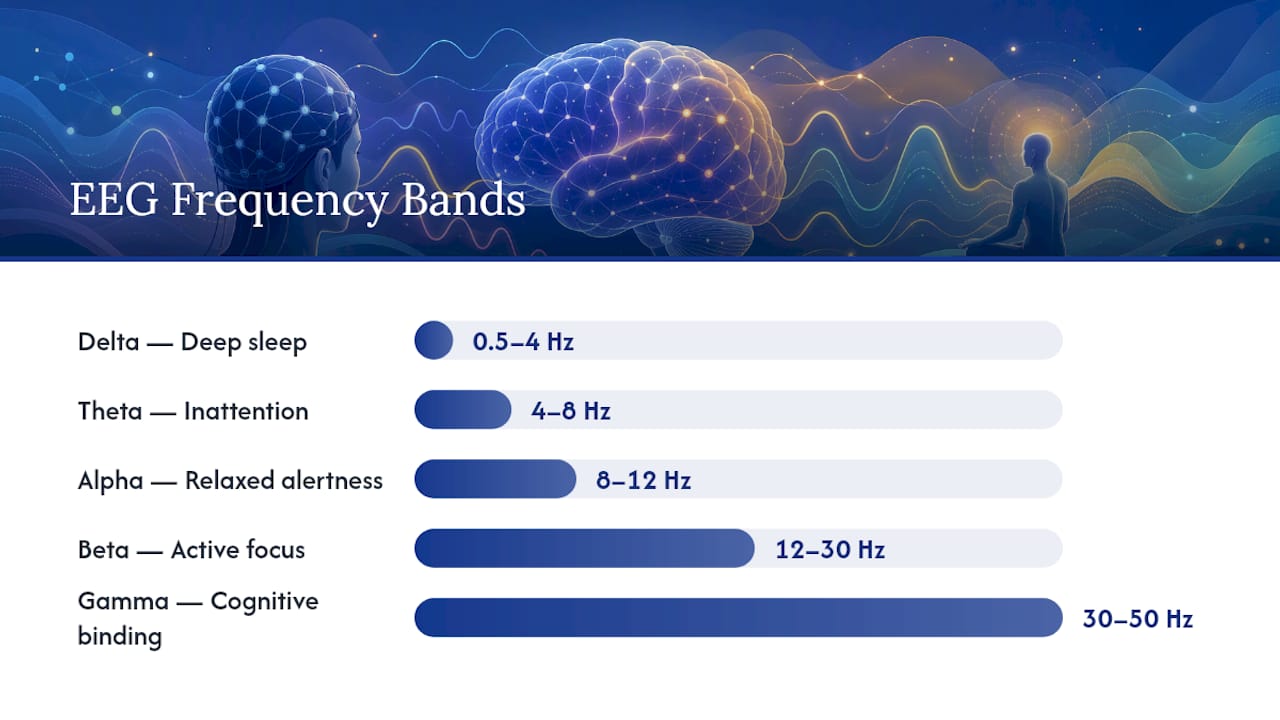
Each brainwave frequency band reflects a different state of neural processing:
| Band | Range | What it reflects |
|---|---|---|
| Delta | 0.5 to 4 Hz | Deep sleep, regenerative processes; elevated during waking in some ADHD profiles |
| Theta | 4–8 Hz | Drowsiness, inattention, memory encoding; often elevated frontally in ADHD |
| Alpha | 8–12 Hz | Relaxed alertness, idle cortex; reduced alpha can indicate anxiety or hyperarousal |
| Beta | 12–30 Hz | Active thinking, focus, motor control; reduced in many ADHD presentations |
| Gamma | 30 to 50 Hz | High-level cognitive binding; less commonly targeted in clinical ADHD protocols |
qEEG versus structural MRI and fMRI
Structural MRI shows brain anatomy. Functional MRI (fMRI) measures blood-flow changes as a proxy for neural activity, with excellent spatial resolution but poor temporal resolution. qEEG captures electrical activity in real time, with millisecond precision, making it uniquely suited to measuring the dynamic, moment-to-moment regulation problems that characterize ADHD. Its spatial resolution is more limited than fMRI, though computational source-localization methods like LORETA can improve spatial interpretation. For clinical ADHD assessment, qEEG’s temporal precision and relative affordability make it the more practical neuroimaging tool, even if it cannot match fMRI’s anatomical detail.
Which qEEG patterns are most commonly associated with ADHD?
The most replicated finding in qEEG research on ADHD is excess theta power combined with reduced beta power, particularly over frontal and central scalp regions. The theta/beta ratio (TBR), typically measured at the Cz electrode during a resting eyes-open condition, became one of the most studied candidate biomarkers in the field. Theta generally falls in the 4–8 Hz range; beta spans roughly 12–30 Hz. When theta is elevated and beta is suppressed, the pattern suggests the cortex is underactivated relative to age-matched peers, a state that maps onto the inattentive, daydreamy quality many people with ADHD describe.
Common qEEG profiles seen in ADHD
- Cortical hypoarousal: Excess frontal theta, reduced beta. The most frequently reported pattern. Associated with inattention, slow processing, and difficulty sustaining effort.
- Delayed cortical maturation: A pattern resembling a younger brain’s EEG, with diffuse theta excess that may normalize with age in some individuals.
- Cortical hyperarousal: Elevated high-frequency beta or reduced alpha. Less common but associated with anxiety, hyperactivity, and sleep difficulties. Requires a different treatment approach than hypoarousal.
- Elevated total power or delta excess: Seen in some presentations, particularly when sleep disorders or other neurological factors are present.
- Connectivity abnormalities: Reduced or atypical coherence between frontal and striatal networks, reflecting disrupted executive function circuitry.
A note on the theta/beta ratio: TBR is a long-studied but contested biomarker. It is age-dependent, varies across databases, and does not reliably distinguish ADHD from other conditions on its own. Clinicians who rely on TBR alone risk misclassifying patients. The more clinically useful approach treats TBR as one data point within a multivariate profile.
Pro Tip: Ask your clinician whether they use a multivariate qEEG profile or a single-metric index. A single number like TBR tells an incomplete story; a full spectral analysis across multiple sites and conditions gives a much richer picture of how your brain is regulating attention.
The narrative review published in PMC confirms that qEEG can identify these common ADHD-related patterns and support neurofeedback protocol selection, while also noting that heterogeneity across studies and placebo effects limit any diagnostic claims. Subtype identification, rather than categorical diagnosis, is where qEEG earns its clinical value.
What does the research say about qEEG and neurofeedback for ADHD?
The evidence base for qEEG-guided neurofeedback in ADHD is genuine but nuanced. Systematic and narrative reviews consistently find that qEEG identifies meaningful electrophysiological differences in ADHD populations and that neurofeedback produces measurable symptom improvements in many patients. The critical question is how large those effects are and how much of the benefit is specific to the brain training itself.
Where the evidence is strongest
qEEG’s clearest contribution is in subtyping and treatment planning. Research supports the idea that identifying a patient’s electrophysiological profile, whether hypoarousal, delayed maturation, or hyperarousal, allows clinicians to select neurofeedback protocols that target the right frequency bands. This precision approach aligns with broader trends in psychiatry: research published in Nature Medicine demonstrates that standardized circuit quantification can identify biotypes that predict treatment response, supporting a precision-medicine framework that translates directly to electrophysiological measures like qEEG.
Functional connectivity neurofeedback studies add further support. Research in Translational Psychiatry shows that targeted normalization of functional connectivity can reduce specific symptom domains, and that optimizing parameters such as consecutive training days and reinforcement schedules improves outcomes. This suggests that when neurofeedback is protocol-matched to a patient’s actual brain profile, results are more consistent.
Where the evidence is mixed
- Placebo effects are real. Some literature reports a substantial short-term symptom improvement in control conditions, which means not all gains attributed to neurofeedback reflect specific neurological change.
- Protocol heterogeneity across studies makes direct comparisons difficult. Different electrode sites, frequency targets, session lengths, and reinforcement methods produce results that are hard to pool.
- The NEBA System, an EEG-based tool that received FDA marketing authorization for use as an aid in evaluating children for ADHD, has faced scrutiny. Studies and reviews have questioned its broad diagnostic reliability and the age-range constraints that limit its generalizability.
The AAN guideline reflects this complexity directly: qEEG should inform clinical decisions as an adjunct, not replace the comprehensive clinical evaluation that remains the gold standard for ADHD diagnosis.
What this means for you
If a provider tells you a qEEG scan will definitively diagnose ADHD, that claim exceeds what the evidence supports. If a provider uses qEEG to refine a diagnosis already established through clinical interview, rating scales, and history, and then uses those findings to personalize your treatment plan, that is exactly the appropriate application.
How clinicians use qEEG to guide treatment choices
The practical value of a qEEG report lies in what happens after the recording. A well-interpreted qEEG maps your brainwave profile to a treatment pathway, most commonly a neurofeedback protocol, but also informing medication decisions and tracking change over time.
From qEEG subtype to neurofeedback protocol
Different electrophysiological profiles call for different training targets. The table below outlines the general mapping clinicians use:
| EEG subtype | Typical neurofeedback protocol | Primary clinical targets |
|---|---|---|
| Cortical hypoarousal (excess theta, low beta) | Theta/beta training (inhibit theta, reward beta at Cz/Fz) | Sustained attention, processing speed, impulse control |
| Delayed cortical maturation (diffuse theta excess) | Theta/beta or SMR training, adjusted for developmental stage | Attention regulation, cortical activation |
| Cortical hyperarousal (excess high-beta, low alpha) | SMR or alpha/theta training (reward SMR or alpha) | Anxiety reduction, sleep quality, emotional regulation |
| Frontal connectivity abnormalities | Slow cortical potential (SCP) training or connectivity-targeted protocols | Executive function, working memory, response inhibition |
Neurofeedback research supports this subtype-to-protocol mapping, with cluster analyses identifying EEG-defined subtypes that align with different training targets.
The clinical workflow
A typical qEEG-guided treatment pathway looks like this:
- Intake and clinical interview: Comprehensive history, standardized rating scales, and behavioral assessment establish the clinical picture.
- qEEG acquisition: Resting and task recordings are collected, processed, and compared against a normative database.
- Clinician interpretation: A qualified professional reviews the topographic maps and spectral data to identify the patient’s electrophysiological subtype.
- Treatment selection: The qEEG profile informs whether neurofeedback, medication adjustment, TMS therapy, or a combination is most appropriate.
- Baseline tracking: The initial qEEG serves as a measurable reference point.
- Follow-up qEEG: After a defined course of treatment (often 20–40 neurofeedback sessions), a repeat recording shows whether the targeted frequency patterns have shifted toward normative ranges.
Non-neurofeedback uses of qEEG
qEEG findings can also inform medication decisions. A hypoarousal profile may support the rationale for stimulant medication, while a hyperarousal pattern might prompt a closer look at non-stimulant options or co-occurring anxiety. Clinicians also use serial qEEGs to measure objective neurological change, which is particularly useful when subjective symptom reports are inconsistent or when a patient wants to see concrete evidence of progress. For patients interested in neurofeedback brain training, the qEEG is the map that makes the training precise rather than generic.
What to expect from a qEEG appointment
Knowing what to expect makes the experience far less daunting. A qEEG session is non-invasive, painless, and typically completed in a single appointment, though the full report usually takes a few days to prepare.
Before your appointment: preparation checklist
- Wash your hair the night before or the morning of your appointment. Avoid conditioners, oils, or styling products, which increase scalp impedance and degrade signal quality.
- Sleep normally. Sleep deprivation significantly alters brainwave patterns and can skew results.
- Discuss medications with your provider in advance. Some clinicians ask patients to take their usual medications to capture a medicated baseline; others prefer an unmedicated recording. Follow your provider’s specific guidance.
- Avoid caffeine for at least 4 hours before the session, as stimulants shift frequency distributions.
- Arrive relaxed. Anxiety and muscle tension introduce artifact into the recording.
During the session
An EEG technologist will measure your head and place a cap or individual electrodes at standardized sites. Conductive gel is applied to each electrode. You will sit quietly with your eyes closed, then eyes open, for several minutes each. If task recordings are included, you may read a passage, complete a simple math task, or respond to a continuous performance test. The recording itself typically takes 20–40 minutes. The technologist monitors the signal in real time and may ask you to relax your jaw or blink normally to reduce artifact.

Timeline and cost
Report delivery generally takes 3–7 business days after the recording, depending on the clinic’s workflow and whether source localization analysis is included. Cost varies considerably by provider and region. A full qEEG assessment with clinical interpretation typically ranges from several hundred to over a thousand dollars out of pocket. Insurance coverage is inconsistent: some plans cover qEEG when it is part of a diagnostic neurological workup, but coverage for qEEG used primarily to guide neurofeedback is less reliable. Verify your specific benefits before scheduling, and ask the clinic whether they provide a superbill for reimbursement. You can find a practical overview of what to expect from iMind’s brain mapping overview page.
Pro Tip: Ask the clinic whether they use a continuous performance task during recording. A task-state recording captures how your brain responds under cognitive demand, not just at rest, which gives the interpreting clinician a more complete picture of your attention regulation.
How qEEG reports are interpreted and who should read them
A qEEG report is not a simple pass/fail document. It contains multiple layers of data, and the clinical meaning of that data depends heavily on who is reading it and which normative database was used for comparison.
What appears in a qEEG report
- Topographic maps: Color-coded scalp maps showing absolute and relative power in each frequency band, typically displayed as a series of “brain images” from above.
- Absolute and relative power tables: Numerical values for each frequency band at each electrode site, compared against normative z-scores.
- Coherence measures: Values reflecting how synchronized different brain regions are with each other, relevant to connectivity-based ADHD profiles.
- Peak frequency: The dominant frequency within a band, which can shift with arousal state or medication.
- Written clinical interpretation: A narrative summary by the interpreting clinician explaining which findings are clinically significant and what they suggest for treatment.
Normative databases and their limits
The comparison database is the backbone of qEEG interpretation. Widely used databases include the Neuroguide normative database and the LORETA Key database, among others. Database choice matters: a database built on a small or demographically narrow sample can produce misleading z-scores. Ask your provider which database they use, how large it is, and whether it includes an age-matched sample relevant to you. A database with thousands of age-stratified, artifact-free recordings produces more reliable comparisons than one built on a few hundred subjects.
Source localization methods like LORETA can estimate which brain regions are generating surface signals, but their spatial precision still cannot match fMRI. Treat source localization findings as hypothesis-generating rather than definitive anatomical conclusions.
Who should interpret your results
- A board-certified neuropsychologist, neurologist, or psychiatrist with specific training in qEEG analysis and neurofeedback.
- An EEG technologist certified through the American Board of Registration of Electroencephalographic and Evoked Potential Technologists (ABRET) for the recording itself.
- Ideally, a clinician who integrates qEEG findings with your full clinical history rather than interpreting the map in isolation.
A qEEG report interpreted by someone without specialized training can lead to overconfident conclusions or missed nuances. If a clinic offers qEEG but cannot clearly identify the credentials of the person writing the clinical interpretation, that is a meaningful red flag.
When is qEEG most useful, and what should you ask before ordering one?
qEEG adds the most value in specific clinical situations. It is not necessary for every person who receives an ADHD diagnosis, and ordering it as a routine first step in a straightforward case adds cost without proportional benefit.
Scenarios where qEEG is most likely to help
- Treatment-resistant ADHD: You have tried multiple medications or behavioral interventions with limited success, and your clinician wants to understand your neurological profile more precisely.
- Diagnostic complexity: Your presentation includes significant comorbidities such as anxiety, depression, or learning disabilities, making it harder to distinguish which symptoms belong to which condition.
- Planning neurofeedback: You are considering neurofeedback as part of your treatment plan and want the protocol tailored to your specific brainwave profile rather than a generic approach.
- Objective progress tracking: You want measurable neurological data to complement subjective symptom reports over the course of treatment.
- Second opinion or diagnostic clarification: If you are questioning a prior diagnosis or seeking a more thorough evaluation, a qEEG can add one more objective data point. A practical guide on when to seek an ADHD second opinion can help you think through that decision.
Low-value scenarios
qEEG is unlikely to add meaningful clinical value when ADHD symptoms are clear, the diagnosis is straightforward, and a standard treatment plan is working well. Using it as a marketing differentiator rather than a clinical tool is a misapplication.
Red flags to watch for
- A clinic that claims qEEG alone can diagnose ADHD.
- Promises of a “cure” through neurofeedback based solely on a brain map.
- No clear disclosure of the interpreting clinician’s credentials.
- Pressure to purchase a large package of neurofeedback sessions before reviewing your qEEG results.
Questions to ask a provider before scheduling
- What equipment and electrode montage do you use, and how many channels does your system record?
- Which normative database do you use for comparison, and what is its sample size?
- Who interprets the qEEG report, and what are their specific credentials in qEEG and neurofeedback?
- Will you share the full written report with me, or only a verbal summary?
- How will the qEEG findings change my treatment plan? What happens if the results are inconclusive?
- What is the total expected cost, including the recording, interpretation, and any follow-up assessments?
- How many neurofeedback sessions do you typically recommend, and when would we repeat the qEEG to measure progress?
How Imindmental uses brain mapping in clinical practice
At Imindmental, brain mapping is one component of a broader, clinically grounded assessment process, not a standalone product. The workflow begins with a thorough intake: a clinical interview, standardized rating scales, and a review of prior records. qEEG acquisition follows, conducted by trained staff using a multi-channel recording system and a validated normative database. The resulting data is interpreted by credentialed clinicians who integrate the electrophysiological findings with the full clinical picture before making any treatment recommendation.
Treatment recommendations emerging from a qEEG assessment at Imindmental may include:
- Neurofeedback (brain training): Protocol selection is matched to the patient’s specific qEEG subtype, targeting the frequency bands most relevant to their symptom profile.
- Psychiatry and medication management: qEEG findings inform, but do not replace, clinical judgment about medication choices and adjustments. Psychiatry services at Imindmental include comprehensive evaluation and ongoing medication management.
- TMS therapy: For patients whose profiles suggest broader treatment-resistant presentations, TMS is available as part of the treatment plan.
- Therapy and multimodal care: Brain mapping results are shared with the broader care team to support coordinated, individualized treatment.
Imindmental serves patients in Port St. Lucie, Vero Beach, and Stuart, FL, with telehealth integration for follow-up appointments and ongoing care coordination. Follow-up qEEG recordings are scheduled after a defined course of treatment to measure whether targeted brainwave patterns have shifted, giving patients and clinicians an objective marker of progress alongside symptom reports.
Realistic expectations matter as much as the technology
There is a version of the qEEG conversation that oversells the technology, and it does patients a disservice. A brain map is not a verdict. It is one layer of information, and a genuinely useful one when it is interpreted by someone qualified to contextualize it within a full clinical picture.
What I find most meaningful about qEEG in practice is not the technology itself but what it makes possible: a more honest, specific conversation between a patient and their clinician. When someone has been told for years that their ADHD “should” respond to a standard stimulant, and the qEEG reveals a hyperarousal profile that actually argues against that approach, that is a turning point. Not because the scan diagnosed anything, but because it gave the clinical team something concrete to work with.
The limits are real. Placebo effects in neurofeedback trials are substantial. Protocol standardization across the field remains inconsistent. And no database comparison replaces the clinical judgment of a qualified professional who knows the patient. Imindmental’s approach is to hold both of these truths at once: qEEG is worth doing when the clinical question warrants it, and it should always be one part of a larger, collaborative assessment rather than the whole answer.
Brain mapping for ADHD: what Imindmental offers you
If you have been navigating ADHD symptoms that do not respond cleanly to standard treatment, or you are considering neurofeedback and want a protocol grounded in your actual brain activity, Imindmental offers a clear path forward. The clinical team in Port St. Lucie, Vero Beach, and Stuart, FL combines qEEG brain mapping with psychiatry, neurofeedback, and TMS under one coordinated care model. You get a full written qEEG report interpreted by credentialed clinicians, a treatment plan built around your specific electrophysiological profile, and follow-up assessments to track real neurological change over time. That is a meaningfully different experience from a generic ADHD evaluation. To take the next step, schedule a psychiatric evaluation with Imindmental and ask about adding a qEEG assessment to your intake.
Sources
The following sources informed this article. Each is linked to the original publication for readers who want to explore the primary literature.
- Neurofeedback for ADHD: Exploring the Role of Quantitative EEG and Brainwave Modulation – PMC
- Personalized brain circuit scores identify clinically distinct biotypes in depression and anxiety | Nature Medicine
- American Academy of Neurology guideline content
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.

