

Seasonal depression, clinically known as Seasonal Affective Disorder (SAD), is treated with three first-line, evidence-based approaches: light therapy, psychotherapy adapted for SAD (CBT‑SAD), and antidepressant medication. Vitamin D supplementation may serve as an adjunct, though the evidence is mixed. If your symptoms are interfering with work, relationships, or daily functioning, or if you are experiencing suicidal thoughts, contact a clinician promptly. If you are in crisis right now, call or text 988 (Suicide and Crisis Lifeline).
The three first-line treatments for SAD are:
- Light therapy: Daily use of a 10,000-lux light box, typically in the morning
- CBT‑SAD: A structured form of cognitive behavioral therapy adapted for seasonal depression
- Antidepressant medication: SSRIs and bupropion XL (FDA-approved for seasonal prophylaxis)
Key Takeaways
Light therapy, CBT‑SAD, and antidepressant medication are the three evidence-based first-line treatments for seasonal depression, and starting any of them before your typical symptom onset month produces better outcomes than waiting.
| Point | Details |
|---|---|
| First-line treatments | Light therapy (10,000 lux, morning), CBT‑SAD, and antidepressants are the three evidence-based options. |
| Medication timeline | Antidepressants typically take 4–8 weeks to show full benefit; start prophylactic bupropion XL in early fall. |
| CBT‑SAD durability | CBT‑SAD shows durable effects that may persist across subsequent winters, unlike light therapy which requires annual re-use. |
| Red flags requiring urgent care | Suicidal thoughts, severe functional impairment, or signs of mania require immediate clinical attention. |
| Imindmental care pathway | Imindmental offers psychiatry, CBT-trained therapy, TMS, Spravato, and telehealth for Florida residents managing seasonal depression. |
Table of Contents
- How clinicians diagnose SAD and rule out other causes
- What symptoms of seasonal depression look like, and when they start
- Seasonal depression treatment: an overview of your options
- How light therapy works and how to use it safely
- How psychotherapy helps with SAD, especially CBT‑SAD
- Antidepressant medications and seasonal prophylaxis
- Vitamin D and other supplements: what the evidence actually shows
- Daily self-care habits that support your seasonal depression treatment
- When you should see a clinician, and what to expect
- How to prevent seasonal depression before it starts
- Special cautions for bipolar disorder, eye disease, pregnancy, and certain medications
- What to realistically expect: timelines and monitoring your progress
- How Imindmental supports people with seasonal depression
- A clinician’s perspective on what actually helps
- Ready to build your seasonal depression care plan with Imindmental
- Sources
How clinicians diagnose SAD and rule out other causes
A diagnosis of SAD is not simply “feeling down in winter.” Clinicians look for a specific, recurrent pattern: depressive episodes that begin and end at predictable times of year, with full remission during other seasons, across at least two consecutive years. The symptom cluster must meet criteria for major depressive disorder, and the seasonal pattern must be the dominant presentation, not just one episode among many.
During an evaluation, your clinician will take a detailed history of symptom timing, severity, and how symptoms have changed across seasons. They will use validated screening tools, most commonly the PHQ-9, to quantify symptom burden. A medication and substance review helps rule out drug-induced mood changes, and a medical workup, typically including thyroid function tests, screens for medical contributors like hypothyroidism that can closely mimic SAD. Sleep and circadian history, including changes in sleep duration, appetite, and energy across seasons, rounds out the picture.
Red flags a clinician screens for urgently:
- Suicidal ideation or self-harm thoughts
- Severe functional impairment (unable to work, care for yourself, or maintain relationships)
- Signs of mania or hypomania (elevated mood, decreased need for sleep, impulsivity, grandiosity)
- Psychotic symptoms
Mania or hypomania in the history changes the diagnosis and the treatment plan entirely. Antidepressants and light therapy can trigger manic episodes in people with bipolar disorder, making accurate diagnosis before treatment a genuine safety issue.
Questions and tests your clinician may use:
- “When do your symptoms typically start and end each year?”
- “Do you sleep significantly more or less in winter?”
- “Have you ever had a period of unusually elevated mood, decreased need for sleep, or racing thoughts?”
- PHQ-9 or SIGH-SAD symptom rating scale
- Thyroid-stimulating hormone (TSH) blood test
- Vitamin D (25-OH) level
- Complete blood count and metabolic panel as indicated
Distinguishing SAD from nonseasonal or situational depression matters because the treatment priorities differ. A clinician who understands the seasonal pattern can build a plan that addresses both acute relief and prevention.
What symptoms of seasonal depression look like, and when they start
Winter-pattern SAD typically begins in late fall or early winter, often between October and November, and remits in spring, usually by March or April. The symptom profile tends to be distinct from classic depression in several ways.
Common symptoms of seasonal depression:
- Persistent low mood or sadness
- Low energy and fatigue, even after adequate sleep
- Hypersomnia (sleeping significantly more than usual)
- Increased appetite, particularly for carbohydrates and sweets
- Weight gain
- Social withdrawal and loss of interest in activities
- Difficulty concentrating or making decisions
- Feelings of hopelessness or worthlessness
The carbohydrate craving and hypersomnia pattern is a useful clinical marker. Many people with SAD describe feeling as though they are “hibernating,” which reflects real changes in serotonin and melatonin regulation driven by reduced daylight exposure, as Johns Hopkins Medicine notes.
When does seasonal depression start? For most people with winter-pattern SAD, symptoms emerge in October or November and lift naturally by spring. Starting treatment before your typical onset month, rather than waiting until symptoms are fully established, produces better outcomes.
Summer-pattern SAD is less common and less well-studied. Its symptoms tend to run in the opposite direction: insomnia rather than hypersomnia, decreased appetite, agitation, and anxiety rather than low energy. Light therapy is not appropriate for summer-pattern SAD, and management typically involves different strategies, including keeping environments cool and dark and, in some cases, medication. If your low mood peaks in summer, discuss this explicitly with your clinician.
Seasonal depression treatment: an overview of your options
The National Institute of Mental Health identifies four main treatment categories for SAD: light therapy, psychotherapy, antidepressant medication, and vitamin D. Understanding where each fits helps you and your clinician build a plan that matches your symptom severity, history, and circumstances.
Treatment families and their primary roles:
- Light therapy: First-line for winter-pattern SAD; fast onset (days to weeks); used daily during symptomatic months
- CBT‑SAD: First-line psychotherapy option; comparable short-term efficacy to light therapy; durable effects across subsequent winters
- Antidepressant medication (SSRIs, bupropion XL): First-line for moderate-to-severe SAD; prophylactic use starting in fall; 4–8 weeks to full effect
- Vitamin D supplementation: Adjunctive only; corrects deficiency but not a proven primary treatment
- Lifestyle measures: Supportive across all severities; outdoor light, exercise, sleep schedule, social contact
Clinical decision factors shape which option comes first. Symptom severity is the most important: mild-to-moderate SAD often responds well to light therapy and lifestyle changes alone. Moderate-to-severe SAD, or SAD that has not responded to light therapy, typically warrants medication or psychotherapy. Comorbid conditions, particularly bipolar disorder, require psychiatric evaluation before any treatment is started. Patient preference and access matter too. Some people prefer not to take medication; others live far from a CBT-trained therapist but can access telehealth therapy easily.
| Treatment | Typical Use Case | Expected Speed of Effect |
|---|---|---|
| Light therapy | Winter-pattern SAD, first-line, mild-to-moderate | Days to weeks |
| CBT-SAD | Any severity; preferred when durability matters | Weeks to months |
| SSRIs | Moderate-to-severe; prior non-response to light therapy | 4–8 weeks |
| Bupropion XL | Seasonal prophylaxis; starting fall, continuing through spring | 4–8 weeks; preventive |
| Vitamin D | Adjunct when deficiency confirmed | Variable; not primary |
| Exercise and lifestyle | Supportive at all severity levels | Days to weeks |
For a broader look at evidence-based depression treatment approaches, including how SAD fits within the wider spectrum of depressive conditions, that resource provides useful context.
How light therapy works and how to use it safely
Light therapy has been a clinical mainstay for winter-pattern SAD since the 1980s. The mechanism centers on the circadian system: bright light in the morning suppresses melatonin, shifts the circadian phase, and appears to increase serotonin availability, addressing the neurochemical disruption that reduced winter daylight triggers. Peer-reviewed clinical analyses confirm bright light therapy at 10,000 lux as an evidence-based treatment for winter-pattern SAD, with a safety profile that makes it suitable for most people without significant eye disease or bipolar history.
| Parameter | Recommended Standard |
|---|---|
| Lux level | 10,000 lux |
| Session length | 20–30 minutes |
| Timing | Within the first hour of waking; morning strongly preferred |
| Frequency | Daily throughout symptomatic months |
| Distance from device | Per manufacturer specification |
The timing detail matters more than most people realize. Morning light therapy aligns with the circadian phase-advance mechanism that makes it effective. Evening use can delay your sleep phase and worsen insomnia, which is already a concern for some SAD presentations.
Safety considerations and contraindications:
- Bipolar disorder: Light therapy can trigger hypomania or mania; use only under psychiatric supervision
- Retinal disease or recent eye surgery: Consult an ophthalmologist before starting
- Photosensitizing medications: Certain antibiotics (tetracyclines), antipsychotics, and St. John’s wort increase light sensitivity; review your medication list with a clinician
- Migraine with light sensitivity: May worsen with bright light exposure; discuss with your provider
- Pregnancy: Generally considered low-risk, but clinician guidance is recommended
When selecting a light box, look for a device that delivers a verified 10,000 lux at the recommended distance, filters UV light, and has an adjustable angle. Manufacturer specifications vary, and a box that delivers 10,000 lux at 12 inches may deliver far less at 24 inches. Devices marketed for “mood” or “energy” without lux specifications are not reliable clinical tools.
Pro Tip: Place your light box at the breakfast table or beside your laptop. Using it while you eat, read, or check email removes the barrier of “finding time” for it and makes daily adherence far more sustainable than treating it as a separate task.
Common side effects are mild and usually transient: headache, eyestrain, nausea, or agitation. If agitation or mood elevation occurs, reduce session length or stop and contact your clinician.
How psychotherapy helps with SAD, especially CBT‑SAD
Cognitive behavioral therapy adapted for seasonal depression, known as CBT‑SAD, is one of the most well-supported psychotherapy options for this condition. It targets two interconnected problems: the negative, season-specific thoughts that sustain low mood (“winter is unbearable,” “I’ll never feel better until spring”) and the behavioral withdrawal that deepens it.
CBT‑SAD typically combines cognitive restructuring with behavioral activation. Cognitive restructuring helps you identify and challenge automatic thoughts tied to the season. Behavioral activation counters the withdrawal and inactivity that come with low energy by scheduling meaningful, mood-lifting activities even when motivation is absent. Activity scheduling and relapse-prevention planning, including preparing for the next winter before symptoms return, are also core components.
A standard CBT‑SAD course runs 6–12 weeks, often with twice-weekly sessions in the early phase. It can be delivered individually, in group format, or via teletherapy. Group delivery has been used in several trials and offers the added benefit of social connection, which is itself a protective factor against SAD.
NIMH reports that CBT‑SAD and light therapy produce similar short-term symptom improvement, with CBT‑SAD showing durable effects that may persist across subsequent winters. Light therapy tends to produce faster initial relief, which makes it a practical first step for acute symptoms. CBT‑SAD’s durability advantage makes it particularly valuable for people who want to reduce reliance on devices or medication over time, or who have had multiple recurrent episodes.
Questions to ask a therapist before starting:
- Do you have experience treating seasonal affective disorder specifically?
- Are you trained in CBT‑SAD or behavioral activation for depression?
- How do you track symptom progress during treatment?
- What does a typical session look like, and how many sessions do you recommend?
- Do you offer teletherapy if I can’t attend in person?
| Dimension | Light Therapy | CBT‑SAD |
|---|---|---|
| Speed of initial relief | Days to weeks | Weeks to months |
| Durability across winters | Requires annual re-use | May persist without re-treatment |
| Delivery mode | Self-administered at home | Requires trained therapist |
| Suitable for bipolar history | Use with caution; supervision needed | Generally safe; monitor mood |
| Access | Device purchase; no appointment needed | Requires therapist availability |
Antidepressant medications and seasonal prophylaxis
Medication is a well-established option for moderate-to-severe SAD and for people who have not responded adequately to light therapy or psychotherapy alone. Two main classes are used.
SSRIs (selective serotonin reuptake inhibitors) such as sertraline, fluoxetine, and escitalopram are commonly prescribed for SAD. They work by increasing serotonin availability in the brain and are effective across depressive conditions, including seasonal presentations. They are not specifically FDA-approved for SAD as a distinct indication, but their use is well-supported by clinical evidence and guidelines.
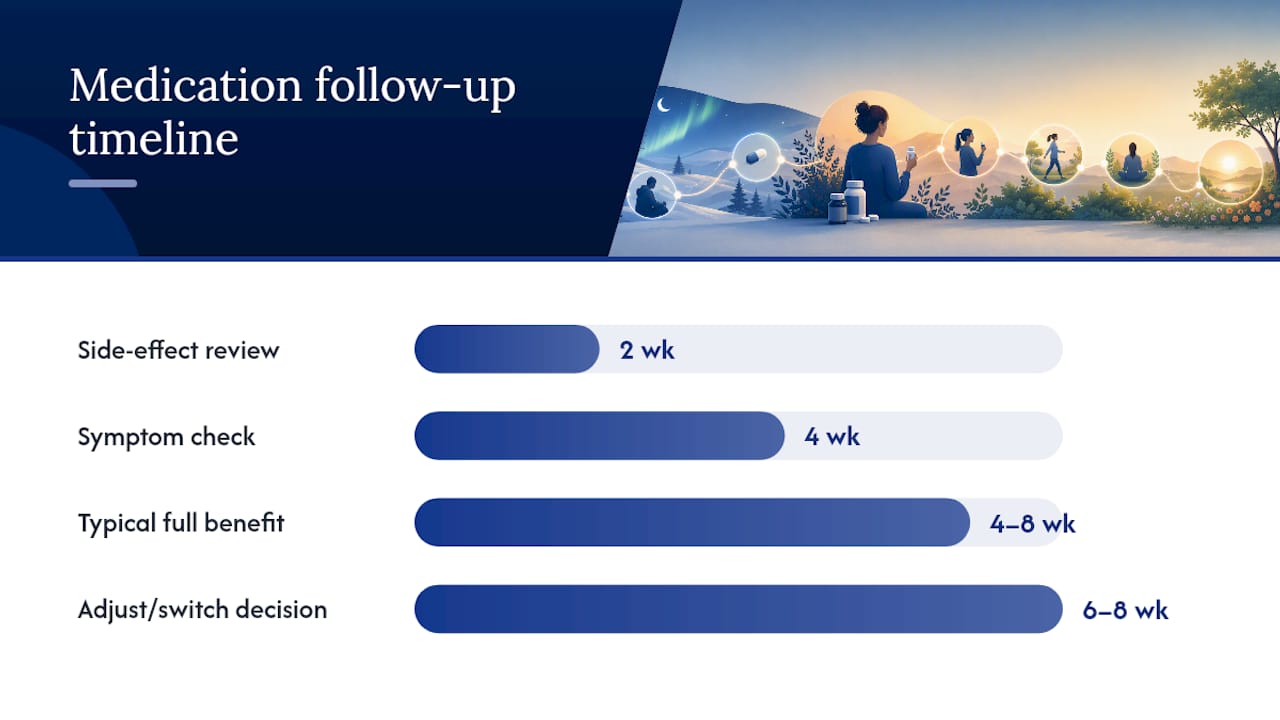
Bupropion XL (extended-release) holds FDA approval specifically for the prevention of seasonal depressive episodes. Cleveland Clinic notes that bupropion XL is taken from fall through early spring as a prophylactic strategy, with antidepressants typically taking 4–8 weeks to show full benefit. This timeline has a practical implication: starting medication after symptoms are already severe means waiting another month or more for meaningful relief. Starting prophylactically, before your typical onset month, avoids that gap.
Medication safety and side-effect checklist:
- SSRIs: common early side effects include nausea, insomnia, headache, and sexual dysfunction; most improve within 2–4 weeks
- Bupropion XL: may cause insomnia, dry mouth, or increased anxiety; lowers seizure threshold at high doses
- Both classes: do not stop abruptly; taper under clinician guidance
- Bipolar history: antidepressants can trigger mania or hypomania; psychiatric evaluation is required before prescribing
- Pregnancy and breastfeeding: discuss risk-benefit with your prescriber; some SSRIs have more safety data than others in this context
- Drug interactions: review all current medications, including supplements like St. John’s wort, with your clinician
Monitoring checklist during medication treatment:
- PHQ-9 or equivalent symptom scale at each follow-up
- Side-effect review at 2 weeks, 4 weeks, and each subsequent visit
- Sleep quality and appetite tracking
- Mood stability monitoring, particularly for any signs of elevated mood or impulsivity
- Plan for dose adjustment or switching if no meaningful improvement after 6–8 weeks
Understanding the benefits of medication management for depression, including how structured follow-up improves outcomes, can help you get the most from a medication-based approach.
Vitamin D and other supplements: what the evidence actually shows
Vitamin D deficiency is common in people with winter-pattern SAD, partly because reduced sunlight exposure limits the skin’s ability to synthesize it. Correcting a confirmed deficiency is reasonable and may support mood, but supplementation is not a proven primary treatment for SAD on its own.

The evidence is genuinely mixed. NIMH cautions that supplements should not replace first-line SAD treatments, and that guidance reflects the current state of the evidence accurately.
What the evidence shows for common supplements:
- Vitamin D: Correct deficiency under clinician supervision; not a standalone SAD treatment
- Melatonin: Small, inconsistent studies; no clear recommendation for routine use in SAD
- St. John’s wort: Some antidepressant effect in mild depression, but significant drug interactions (including with SSRIs and photosensitizing effects); not recommended alongside other SAD treatments without clinician review
- Vitamin B12: No clear evidence for SAD specifically
- Ginkgo biloba: Insufficient evidence; not recommended for SAD
The practical takeaway is straightforward: ask your clinician to check your 25-OH vitamin D level, correct any deficiency with an appropriate dose, and treat supplementation as supportive rather than primary. Do not substitute supplements for light therapy, CBT‑SAD, or medication if those treatments are indicated.
Pro Tip: If you are already taking St. John’s wort and considering light therapy or an SSRI, tell your clinician before starting either. St. John’s wort increases photosensitivity and carries a real risk of serotonin syndrome when combined with SSRIs.
Daily self-care habits that support your seasonal depression treatment
Self-care measures do not replace clinical treatment for moderate-to-severe SAD, but they meaningfully support it at every severity level. The most effective habits target the same biological systems that SAD disrupts: circadian rhythm, serotonin, and behavioral engagement.
Building a morning routine that works
- Get outside within 30–60 minutes of waking. Even on overcast days, outdoor light is significantly brighter than indoor lighting and provides circadian input. UR Medicine recommends combining morning light therapy with outdoor daylight exposure as complementary strategies.
- Keep your wake time consistent, including weekends. Irregular sleep timing destabilizes circadian rhythms and worsens mood. A consistent anchor time is one of the simplest and most effective adjustments you can make.
- Use a sunrise alarm clock. Gradual light increase before your alarm mimics dawn and eases the transition out of sleep, particularly useful in dark winter months.
- Schedule at least one social contact per day. Even brief, low-effort connection, a phone call, a short walk with a friend, counters the social withdrawal that deepens SAD symptoms.
- Plan exercise in the morning or early afternoon. Physical activity boosts serotonin and dopamine, and timing it earlier in the day aligns with circadian benefits. Aim for at least 30 minutes of moderate activity most days.
Environment and workplace adjustments
- Rearrange your workspace to sit near a window, or face a window during the hours of peak daylight.
- Schedule important meetings, calls, or focused work during the brightest part of the day (typically 10 AM to 2 PM in winter).
- Use warm, bright indoor lighting in living areas during evening hours to reduce the contrast between indoor and outdoor environments.
Practical daily habits that support SAD management:
- Eat regular meals to stabilize blood sugar and reduce carbohydrate craving cycles.
- Limit alcohol, which disrupts sleep architecture and worsens depressive symptoms.
- Keep a brief daily mood and sleep log; patterns become visible quickly and are useful at clinical appointments.
Building a personalized therapy-supporting routine takes consistency over perfection. Missing one morning does not undo progress; the goal is a sustainable structure, not a rigid schedule.
When you should see a clinician, and what to expect
Some symptoms of seasonal depression warrant prompt clinical attention rather than self-management. Knowing the difference protects you.
Seek care urgently if you experience:
- Suicidal thoughts or thoughts of self-harm (call or text 988 immediately, or go to your nearest emergency room)
- Severe functional impairment: unable to work, attend school, or care for yourself or dependents
- Signs of mania or hypomania: elevated or irritable mood, significantly decreased need for sleep, racing thoughts, impulsive behavior
- Psychotic symptoms: hallucinations, paranoia, or beliefs disconnected from reality
- Symptoms that are worsening rapidly despite self-care efforts
For a routine SAD evaluation, knowing what to expect makes the appointment more productive. Your clinician will take a full psychiatric history, administer a symptom rating scale, review your medications and supplements, and may order blood work (thyroid, vitamin D, CBC). They will ask about prior treatment responses and any personal or family history of bipolar disorder. Recognizing the signs of clinical depression before your appointment helps you describe your experience accurately.
Appointment preparation checklist:
- Write down when your symptoms typically start and end each year, and how long this pattern has been present.
- Note your current sleep pattern: hours per night, wake time, and any changes from your non-symptomatic baseline.
- List all current medications, supplements, and their doses.
- Record any prior treatments for depression or SAD and whether they helped.
- Bring a list of questions, including those about treatment options, timelines, and what to do if a treatment is not working.
- Note any personal or family history of bipolar disorder, mania, or psychosis.
How to prevent seasonal depression before it starts
Prevention is not just for people who have had severe episodes. Anyone with a reliable seasonal pattern can reduce the severity of future episodes, and sometimes prevent them entirely, by acting before symptoms arrive.
A pre-season preparation checklist
- Start light therapy before your typical onset month. If your symptoms usually begin in November, start your light box in early October. Waiting until you feel bad means waiting another week or two for the therapy to take effect.
- Schedule therapy or booster sessions in advance. If you have done CBT‑SAD before, a few booster sessions in early fall can reinforce the skills before the season begins.
- Optimize your sleep and exercise routines before fall. Consistent habits are easier to maintain than to establish when energy is already low.
- Check your vitamin D level in September. Correcting a deficiency before winter reduces one contributing factor early.
- Discuss prophylactic medication with your prescriber. For people with a reliable history of moderate-to-severe SAD, starting bupropion XL in early fall, before symptoms emerge, is a clinically supported strategy.
Ongoing prevention habits:
- Keep your morning light exposure routine year-round at a lower intensity, rather than stopping abruptly in spring.
- Maintain social commitments and exercise schedules through fall, even when motivation starts to dip.
- Track your mood with a simple daily rating (1–10) starting in September; early warning signs are easier to act on than established symptoms.
- Coordinate with your prescriber about when to taper medication in spring, typically after several weeks of consistent remission.
Consistency across seasons is what separates effective prevention from reactive management. Initiating light therapy or prophylactic medication before expected onset, and continuing through spring, prevents recurrence more reliably than starting treatment only after symptoms are fully established.
Special cautions for bipolar disorder, eye disease, pregnancy, and certain medications
Not everyone can use standard SAD treatments without modification. Several populations require clinician coordination before starting light therapy or antidepressants.
Population-specific cautions:
- Bipolar disorder (any type): Both light therapy and antidepressants carry a real risk of triggering hypomania or mania. Psychiatric supervision is required before starting either. Mood stabilizers are typically the foundation of treatment in this group, with any SAD-specific therapy added carefully and monitored closely.
- Retinal disease or recent eye surgery: Conditions such as macular degeneration, glaucoma, or diabetic retinopathy may be worsened by bright light exposure. Consult an ophthalmologist before using a light box.
- Photosensitizing medications: Tetracycline antibiotics, certain antipsychotics, some diuretics, and St. John’s wort all increase light sensitivity. Review your full medication list with your clinician before starting phototherapy.
- Pregnancy and breastfeeding: Light therapy is generally considered low-risk and is often preferred over medication in this context, but clinician guidance is still recommended. For medication, the risk-benefit discussion with your prescriber should include the specific agent, trimester, and breastfeeding status, as safety profiles vary.
- Migraine with photophobia: Bright light may trigger or worsen migraines in some people; discuss with your neurologist or primary care provider.
Always tell your clinician about any mood instability, eye conditions, or photosensitizing medications before starting phototherapy or a new antidepressant. This is not a formality; it directly shapes which treatment is safe for you.
Pro Tip: If you have a personal or family history of bipolar disorder and have never been formally evaluated, a psychiatric assessment before starting any SAD treatment is the single most important safety step you can take. Undiagnosed bipolar disorder is one of the most common reasons SAD treatment causes unexpected problems.
When standard treatments are contraindicated, alternative approaches include structured behavioral activation without medication, mindfulness-based cognitive therapy (MBCT), and, for treatment-resistant cases, neuromodulation options such as TMS therapy or Spravato, which are available at specialty clinics.
What to realistically expect: timelines and monitoring your progress
Treatment for seasonal depression does not work overnight, and knowing the typical timeline prevents premature discouragement.
| Treatment | Typical Onset of Benefit | Full Effect | Notes |
|---|---|---|---|
| Light therapy | Days to 1–2 weeks | 2–4 weeks of daily use | Requires consistent morning use; stop in spring |
| CBT-SAD | 3–4 weeks | 6–12 weeks | Durable gains may persist across winters |
| SSRIs | 2–4 weeks (partial) | 4–8 weeks | Full benefit requires consistent dosing |
| Bupropion XL (prophylactic) | 4–8 weeks | Ongoing through spring | Start before symptom onset in fall |
| Lifestyle measures | Days to weeks | Ongoing | Supportive; enhances other treatments |
Mayo Clinic emphasizes that most SAD treatments require several weeks of consistent adherence to show meaningful improvement. Stopping light therapy after a week because you “don’t feel different yet” is one of the most common reasons treatment appears to fail.
Monitoring checklist for tracking your progress:
- Complete a PHQ-9 every 2–4 weeks and share results with your clinician.
- Keep a brief sleep diary: bedtime, wake time, total hours, and morning energy rating.
- Log side effects from medication at each follow-up visit.
- Note any mood elevation, agitation, or sleep changes that feel unusual, as these may indicate a need to adjust treatment.
- Schedule follow-up appointments at 2 weeks, 4 weeks, and 8 weeks after starting a new treatment.
If you have completed an adequate trial (typically 4–6 weeks of consistent use for light therapy, 6–8 weeks for medication) without meaningful improvement, discuss with your clinician whether to adjust the dose, add a second treatment, or switch approaches. Combined therapy, light therapy plus CBT-SAD, or light therapy plus medication, is a reasonable next step for partial responders. For treatment-resistant seasonal depression, neuromodulation options including Deep TMS and Spravato represent evidence-supported escalation steps available at specialty clinics.
How Imindmental supports people with seasonal depression
Imindmental (iMind Mental Health Solutions) is a Florida-based, veteran-owned mental health practice offering a full range of evidence-based SAD treatments across in-person and telehealth formats. Whether you are seeking an initial evaluation, a medication review, or a structured therapy program, the care pathway is designed to be accessible and coordinated.
Services relevant to seasonal depression management:
- Psychiatry and medication management: Evaluation, SSRI prescribing, bupropion XL prophylaxis, and ongoing monitoring
- Psychotherapy: CBT-trained therapists offering individual and structured therapy approaches for seasonal depression
- TMS (Transcranial Magnetic Stimulation): A non-medication neuromodulation option for treatment-resistant depression
- Spravato (esketamine): An FDA-approved treatment for treatment-resistant depression, available at Imindmental’s Florida locations
- Telehealth: Secure video appointments for therapy and psychiatry, available to Florida residents statewide
- In-person care: Locations in Port St. Lucie, Vero Beach, and Stuart, FL
Imindmental accepts many insurance plans and offers rapid appointment booking with insurance verification support. If you are preparing for your first visit, bring a written symptom timeline, your current medication list, and any prior treatment history. The team-based integrated care model at Imindmental means your therapist, prescriber, and care coordinator work together rather than in isolation, which matters when managing a condition that often requires combined treatment.
For veterans and first responders managing seasonal depression alongside other mental health concerns, Imindmental offers tailored treatment pathways. You can learn more about mental health treatment options for veterans and families in Florida through their dedicated resource.
A clinician’s perspective on what actually helps
What I see most often is not treatment failure. It is treatment abandonment. Someone starts light therapy in November, feels better by December, and stops using it by January because the routine slips. Or they start an antidepressant, feel partial improvement at four weeks, and assume it is not working before the full effect has had time to develop. The biology of seasonal depression responds to consistency, not intensity.
The other pattern worth naming is the tendency to wait. People often recognize their seasonal pattern for years before seeking an evaluation, telling themselves it is “just winter” or “not bad enough yet.” By the time they come in, they have lost months of productive time and the window for prophylactic treatment has already closed. Starting a conversation with a clinician in September, before symptoms arrive, is almost always more effective than starting in December when you are already struggling.
The evidence supports combining approaches when one is not enough. Light therapy plus CBT-SAD, or light therapy plus medication, outperforms any single treatment for many people with moderate-to-severe SAD. A personalized plan, built with a clinician who knows your history, is the most reliable path to a better winter.
Ready to build your seasonal depression care plan with Imindmental
If your symptoms follow a seasonal pattern and are affecting your quality of life, a psychiatric evaluation is the clearest next step. Imindmental’s psychiatry services cover the full spectrum of SAD care: initial evaluation, medication management, prophylaxis planning, and coordination with therapy.
How to get started:
- Telehealth: Available to Florida residents statewide; book a video appointment for psychiatry or therapy without traveling
- In-person: Locations in Port St. Lucie, Vero Beach, and Stuart, FL
- Insurance: Imindmental verifies insurance coverage at intake; bring your insurance card and a list of current medications
- What to expect: A thorough intake covering your symptom history, seasonal pattern, prior treatments, and goals; a collaborative treatment plan developed with you, not handed to you
For those exploring what mental health support looks like in 2026, including telehealth options and how to choose the right level of care, that resource offers useful context alongside Imindmental’s own services.
Book your evaluation at Imindmental and come prepared with your symptom timeline, medication list, and questions. The earlier in the season you start, the more options you have.
Sources
The following clinical resources provide the evidence base behind the recommendations in this article. Each covers a distinct aspect of SAD diagnosis and treatment.
- Seasonal Affective Disorder – National Institute of Mental Health (NIMH)
- Treatment of seasonal affective disorders – PMC – NIH
- How to fight the winter blues and SAD this season – UR Medicine
These sources are starting points, not substitutes for clinical advice. A clinician who knows your full history can interpret these findings in the context of your specific situation and build a treatment plan accordingly.
This article provides general health information and is not a substitute for professional medical advice. Please consult a qualified clinician for diagnosis, treatment recommendations, and guidance specific to your situation.

