

Shift work sleep disorder is a circadian rhythm condition that causes insomnia, excessive sleepiness, or both when your work hours conflict with your body’s internal clock. If your daytime sleep feels broken and your energy crashes on the job, start by anchoring your sleep and wake times, controlling light exposure, and talking to a clinician if the problem lasts more than a few weeks.
TL;DR:
- Keeping sleep and wake times consistent, especially on days off, is essential to prevent circadian misalignment related to shift work sleep disorder.
- Strategic light exposure during night shifts and blackout curtains for daytime sleep can significantly improve alertness and sleep quality.
- Timed use of melatonin and naps can help manage sleep timing and reduce fatigue, but both require proper planning and, ideally, clinician guidance.
- Managing shift work sleep disorder effectively involves a layered approach, including schedule adjustments, behavioral therapy, and medication if necessary.
- Persistent symptoms after several weeks of self-management warrant clinical evaluation to rule out other sleep disorders and develop personalized treatment plans.
Table of Contents
- What Is Shift Work Sleep Disorder and How Common Is It?
- Symptoms and What Actually Causes Shift Work Insomnia
- How Is Shift Work Sleep Disorder Diagnosed?
- Treatment Options: What Actually Helps You Sleep Better on Shifts
- What’s the Long-Term Outlook for Shift Work Sleep Disorder?
- Building a Sleep-Friendly Life Around Your Shift Schedule
- The Gap Between “Push Through It” and What Actually Works
- Getting Clinical Support for Shift Work Sleep Disorder
- Sources
What Is Shift Work Sleep Disorder and How Common Is It?
Your body runs on two overlapping systems: a circadian clock that tells you when to feel alert or drowsy based on light and darkness, and a homeostatic sleep drive that builds pressure to sleep the longer you stay awake. When these two systems work together, you fall asleep easily at night and wake up refreshed. Night, early-morning, and rotating shift schedules pull them apart. You might be biologically primed for alertness right when you’re trying to fall asleep at 8 a.m., or fighting a wave of sleepiness at 3 a.m. when your body expects you to be in deep sleep.
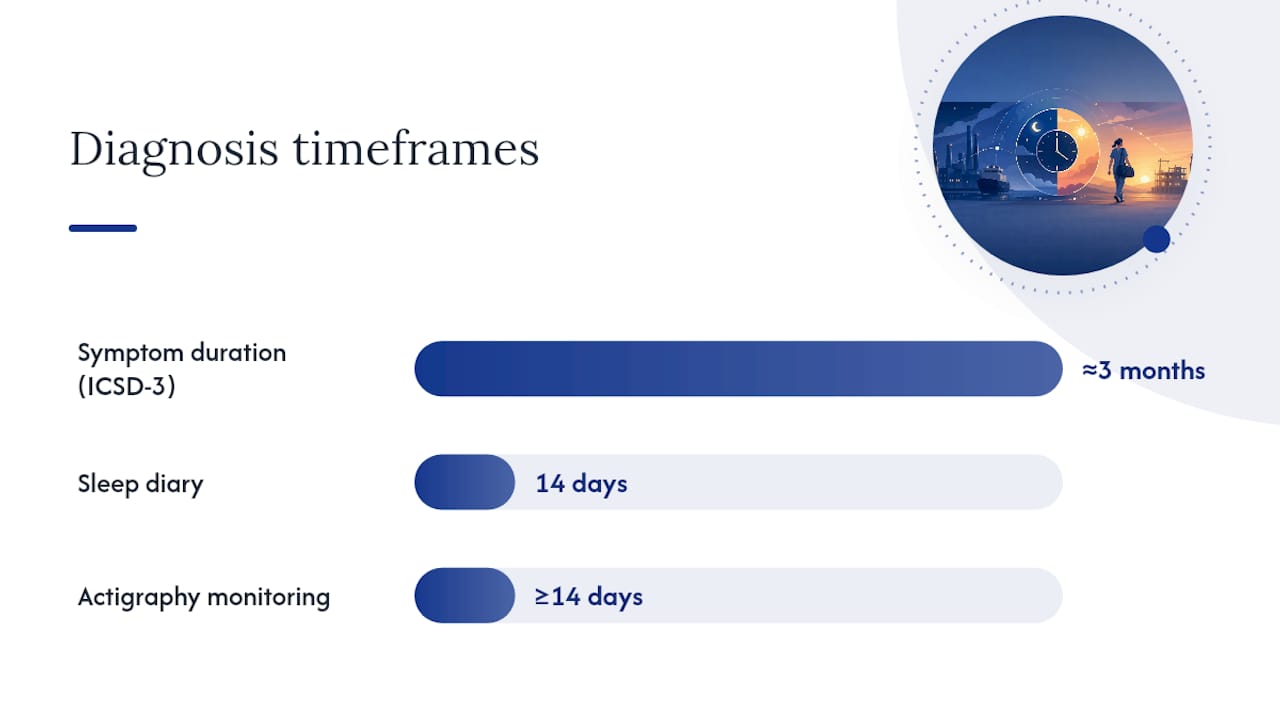
That mismatch, when it becomes persistent, has a name. According to research published in PMC, shift work sleep disorder is a circadian rhythm sleep disorder marked by insomnia, excessive sleepiness, or both, arising specifically because a person’s work hours overlap with their normal sleep window. The International Classification of Sleep Disorders, Third Edition (ICSD-3) adds a duration requirement: symptoms need to persist for roughly three months, and they need to happen alongside your work schedule specifically, not just as a one-off bad week after a schedule change.
This isn’t a rare complaint reserved for a small slice of workers. Reviews summarized in the NCBI Bookshelf put prevalence estimates in a meaningful range, with some sample studies finding around 14% of night workers meet full diagnostic criteria for the disorder, and broader analyses suggesting even higher proportions experience clinically significant sleep disturbance tied to their schedules.
Quick fact: Roughly one in seven night shift workers may meet the clinical threshold for shift work sleep disorder, not just ordinary fatigue, according to sample-based estimates cited by the NCBI Bookshelf.
The people most affected tend to work in healthcare, protective services (police, fire, corrections), transportation, and manufacturing, industries where round-the-clock coverage is non-negotiable. If you rotate shifts frequently, work overnight, or start before 6 a.m. on a regular basis, you’re in the population this condition targets.
Symptoms and What Actually Causes Shift Work Insomnia
Two symptom patterns define shift work sleep disorder, and you may experience one or both. The first is insomnia: trouble falling asleep during your scheduled sleep period, trouble staying asleep, or waking up too early and being unable to get back to sleep. The second is excessive sleepiness during your waking hours, particularly during work shifts, when you may find yourself fighting to stay alert during tasks that demand focus.
Neither symptom on its own confirms the diagnosis. Everyone has a rough night occasionally, and everyone gets tired sometimes. What separates shift work sleep disorder from garden-variety tiredness is duration and pattern. Clinicians generally look for symptoms lasting about three months, occurring specifically in connection with a nontraditional work schedule, and causing real impairment, whether that’s difficulty concentrating, irritability, or errors at work.
Here’s what tends to show up alongside those two core symptoms:
- Difficulty falling asleep even when exhausted, especially during daytime sleep attempts after a night shift
- Fragmented sleep with frequent waking, often triggered by daylight, household noise, or phone notifications
- Sleepiness severe enough to affect driving, decision making, or safety-sensitive tasks
- Mood changes, including irritability, anxiety, or low motivation
- Reliance on caffeine or energy drinks just to get through a shift
- Falling asleep unintentionally during breaks, commutes, or downtime
The causes go beyond simply “working nights.” Rotating schedules are particularly hard on the body because they never let your circadian rhythm settle into a rhythm at all. Insight from reviews of shift work physiology, summarized in PMC, points to circadian misalignment itself, not poor sleep discipline, as the primary driver. That distinction matters for how you approach treatment: no amount of willpower fixes a clock that hasn’t been given the right light and dark cues.
Short recovery intervals between shifts make things worse. Getting less than 11 hours off between one shift and the next doesn’t leave enough time for a full sleep cycle plus commuting, eating, and basic life tasks. Counterclockwise rotations (moving from day to night to evening shifts, for example) tend to be harder on the body than clockwise rotations that move forward through the day.
A few other factors compound the problem. Exposure to bright light on the commute home after a night shift signals your brain that it’s time to be awake, working directly against your attempt to sleep. Alcohol used as a sleep aid tends to fragment sleep later in the cycle. And stimulant use timed too close to your intended sleep period can delay sleep onset by hours.
It’s also worth ruling out overlapping conditions. Obstructive sleep apnea, mood disorders like depression or generalized anxiety, and other primary insomnia disorders can produce symptoms that look similar to shift work sleep disorder or make it worse when both are present. This is one reason self-diagnosis only gets you so far, and why a clinical evaluation matters if symptoms don’t improve with basic schedule adjustments.
How Is Shift Work Sleep Disorder Diagnosed?
Diagnosis starts with a conversation, not a machine. A clinician evaluating you for shift work sleep disorder will walk through the ICSD-3 criteria in a structured way, and understanding that checklist ahead of time can make your appointment far more productive.
- Symptom pattern. Do you have insomnia, excessive sleepiness, or both, occurring in connection with a work schedule that overlaps your normal sleep period?
- Duration. Have these symptoms been present for approximately three months or longer, despite reasonable attempts to adjust your schedule or sleep habits?
- Functional impact. Are the symptoms affecting your work performance, safety, mood, or relationships in a measurable way?
- Exclusion of other causes. Could another sleep disorder, medical condition, or medication better explain what you’re experiencing?
To answer these questions objectively, clinicians usually ask patients to keep a sleep diary. This means logging bedtime, estimated time to fall asleep, number and length of awakenings, final wake time, naps, caffeine intake, and shift schedule, every day, for about two weeks. Findings summarized by the NCBI Bookshelf note that sleep diaries paired with actigraphy, a wrist-worn device that tracks movement to estimate sleep and wake periods, over at least 14 days including both work and non-work days, give clinicians the clearest picture of your actual sleep pattern versus your schedule.
Polysomnography, the overnight, lab-based sleep study most people associate with sleep medicine, usually isn’t required for a shift work sleep disorder diagnosis. It becomes necessary when your clinician suspects a coexisting condition, most commonly obstructive sleep apnea, that needs its own confirmation and treatment plan.
Expect your clinician to also ask about your full shift history: how long you’ve worked nights or rotating shifts, how often your schedule changes, your commute length and light exposure during that commute, caffeine and alcohol habits, and any medications you’re taking. If your case is complicated, involves suspected sleep apnea, or hasn’t responded to initial adjustments, referral to a board-certified sleep medicine specialist is a reasonable next step, and one you shouldn’t hesitate to ask for.
Treatment Options: What Actually Helps You Sleep Better on Shifts
Effective management of shift work sleep disorder follows a logical sequence: fix the schedule and light exposure first, layer in behavioral countermeasures, and reserve medication for cases where symptoms persist despite those changes. The Cleveland Clinic frames this as a stepwise approach, and it matches how sleep medicine specialists typically counsel patients.
Start with schedule consistency
The single biggest lever you have is keeping your sleep and wake times as consistent as possible, including on days off. It sounds simple, but it’s the step most people skip. Insight drawn from shift work research in the NCBI Bookshelf identifies “social jet lag,” the tendency to revert to a normal daytime schedule on your off days, as a major reason circadian misalignment never resolves. Every time you swing back to a conventional schedule for the weekend, you force your body to re-adapt on your next work night.
That doesn’t mean you can never see your family for a Sunday dinner. It means limiting how drastically you shift your sleep window and building recovery sleep into your schedule deliberately, rather than sleeping in six extra hours one day and crashing the next.
Manage light exposure like a medication
Light is the most powerful signal your circadian clock responds to, more powerful than caffeine, more powerful than willpower. If you work nights, seek out bright light during the first part of your shift to promote alertness when you need it most. The AASM’s clinical practice guideline, published in May 2025, issues a conditional recommendation for bright light exposure during night shifts specifically to help manage excessive sleepiness, though the strength of that recommendation varies by individual circumstances.
Just as important: wear dark sunglasses on your commute home. Morning sunlight hitting your eyes tells your brain it’s time to wake up, which is the opposite of what you want right before trying to sleep. Once home, a dark bedroom isn’t optional, it’s a core treatment tool. Blackout curtains, an eye mask, and dimmed lighting in the hour before you attempt sleep all reinforce the same message to your circadian system.
Time melatonin with purpose, not guesswork
Melatonin isn’t a generic sleep aid here; its effect depends heavily on timing. Deep knowledge from shift work management research in PMC explains that melatonin has phase-response characteristics: taken before your desired sleep time, it can shift your clock earlier (phase-advance); taken later, closer to your natural wake time, it can shift your clock later (phase-delay).
For night shift workers trying to sleep during the day, the goal is usually to delay or anchor the sleep episode, which means timing matters more than dose. Taking melatonin at the wrong point in your cycle can actually work against you. This is exactly the kind of detail worth discussing with a clinician rather than experimenting with on your own, since individual response varies and melatonin can interact with other medications.
Use naps and caffeine strategically
A short nap before a night shift, ideally 20 to 30 minutes, taken a couple of hours before you start work, can meaningfully reduce sleepiness during the first half of your shift without leaving you groggy. Caffeine works best when front-loaded: consume it early in your shift rather than in the final hours, since caffeine’s half-life means a coffee at 3 a.m. can still be affecting your system when you’re trying to fall asleep at 8 a.m.
Research on operational fatigue management, described in PMC, found that combining a strategic nap, caffeine, and bright light exposure tends to outperform any single countermeasure for maintaining alertness during night work. Even so, this combination doesn’t fully correct circadian misalignment on its own, it manages symptoms while your body continues adjusting, or fails to adjust, to the schedule.
Watch for sleep inertia, the grogginess and impaired judgment that can follow a nap or waking from deep sleep. If you’re napping right before driving or operating machinery, build in at least 15 to 20 minutes to fully wake up first.
Pro Tip: Set a caffeine cutoff at the midpoint of your shift, not the end of it. If your shift runs midnight to 8 a.m., your last cup of coffee should happen well before 4 a.m. to avoid interfering with your daytime sleep.
Consider CBT-I, with realistic expectations
Cognitive behavioral therapy for insomnia (CBT-I) is the first-line treatment for chronic insomnia in the general population, and many of its techniques, stimulus control, sleep restriction, cognitive restructuring around sleep anxiety, can be adapted for shift workers. That said, evidence specific to shift work populations remains limited. Findings summarized by the NCBI Bookshelf note that while CBT-I is broadly recommended for insomnia, studies focused specifically on shift workers are smaller and less conclusive, so it’s reasonable to view it as a promising option rather than a guaranteed fix. A therapist experienced in behavioral sleep medicine can tailor the standard protocol to your actual schedule instead of a conventional 24-hour day.
Medication: wake-promoting agents and short-acting hypnotics
For persistent excessive sleepiness that doesn’t respond to schedule and light interventions, the AASM’s May 2025 clinical practice guideline suggests wake-promoting agents, specifically modafinil or armodafinil, as a conditional recommendation for adults with shift work disorder. These medications don’t fix circadian misalignment; they help manage alertness during shifts when sleepiness has become a safety concern.
On the insomnia side, short-acting hypnotics are sometimes used cautiously to support daytime sleep, but this requires direct clinician supervision given the potential for side effects, dependency risk, and interactions with other medications or health conditions. The AASM guideline’s own framing is instructive here: as one insight from the guideline notes, most of these recommendations are conditional, meaning clinicians have to weigh your specific preferences, risks, and circumstances rather than applying a single formula to every patient. If you’re managing medication as part of your treatment plan, working with a psychiatric provider who understands medication management for complex, schedule-driven conditions matters more than the specific drug name.
A short summary of where each option fits:
- Schedule and light management: foundational, addresses the root cause, works for nearly everyone
- Timed melatonin: supports sleep onset and timing, requires clinician guidance on dose and timing
- Naps and caffeine: manage symptoms during shifts, don’t fix underlying misalignment
- CBT-I: helps with the insomnia component, evidence in shift workers still developing
- Modafinil/armodafinil: conditional recommendation for persistent daytime sleepiness, prescription required
- Short-acting hypnotics: used cautiously for daytime insomnia, only under medical supervision
One more point that deserves its own emphasis: never drive home after a long shift if you’re experiencing significant sleepiness. Arrange a ride, nap in your car in a safe location first, or use public transit. Workplace fatigue risk controls, things like limiting consecutive night shifts, building in adequate recovery time between shifts, and allowing planned nap breaks, are increasingly recognized as an employer responsibility, not just an individual coping problem.
What’s the Long-Term Outlook for Shift Work Sleep Disorder?
For some people, symptoms improve within weeks of a schedule change, a switch from rotating to fixed shifts, or the consistent application of light and sleep timing strategies. For others, especially those who stay on demanding rotating schedules for years, the condition becomes chronic, and the health stakes rise the longer it goes unaddressed.
Sustained circadian misalignment carries real long-term risk. Review evidence summarized in PMC links chronic circadian disruption to increased risk of metabolic dysfunction, including insulin resistance and weight gain, cardiovascular disease, and mental health conditions such as depression and anxiety. Sleepiness-related accident risk is also elevated among shift workers, both on the job and during the commute home, which is precisely why safety-focused countermeasures aren’t optional extras.
None of this means chronic shift work automatically leads to poor health. It means the body pays a measurable cost for prolonged misalignment, and that cost tends to be smaller the earlier you intervene. If you’ve tried basic schedule and light adjustments for several weeks without improvement, that’s the signal to bring in a clinician rather than waiting to see if things resolve on their own.
Building a Sleep-Friendly Life Around Your Shift Schedule
Managing shift work sleep disorder day to day comes down to controlling what you can control: your sleep environment, your schedule choices where you have any input, and the habits surrounding meals, exercise, and alcohol.
Your bedroom during the day needs to function like nighttime, artificially. That means:
- Blackout curtains or a well-fitted eye mask to eliminate daylight
- A white noise machine or fan to mask household and street noise
- Keeping the room cool, most people sleep best around 65 to 68°F
- A consistent pre-sleep routine, even 15 minutes, to cue your brain that sleep is coming
- Phones on do-not-disturb, not just silent, to avoid light and notification interruptions
Patient education resources from UCLA Health echo many of these same points, alongside practical guidance on timing meals and stimulant use around your actual schedule rather than the clock on the wall.
If you have any say in your schedule, fixed shifts are generally easier on your body than rotating ones, and clockwise rotations (day to evening to night) tend to be gentler than counterclockwise rotations. Push for at least 11 hours between shifts when negotiating your schedule, since shorter turnarounds rarely leave room for adequate sleep plus basic life tasks.
Beyond sleep mechanics, timing your meals to match your work schedule rather than eating heavy meals right before an attempted daytime sleep supports better rest. Regular exercise helps too, though timing it too close to your intended sleep period can be counterproductive. Limit alcohol near bedtime; it may make you feel sleepy initially but tends to fragment sleep later in the cycle.
Finally, don’t underestimate the value of talking directly with your employer about fatigue risk. Many workplaces, particularly in healthcare and transportation, now have formal fatigue management policies. Asking about shift scheduling accommodations, minimum rest intervals, or a switch away from rotating shifts isn’t an unreasonable request. It’s a legitimate health conversation.
The Gap Between “Push Through It” and What Actually Works
The most persistent myth about shift work sleep disorder is that it’s a discipline problem, that people who struggle with night shifts just haven’t tried hard enough to adjust. The research doesn’t support that framing. Circadian misalignment is a physiological reality, not a character flaw, and the interventions that actually move the needle, light timing, melatonin timing, schedule consistency, target the biology directly rather than asking someone to white-knuckle their way through years of fragmented sleep.
What I find most underappreciated in this conversation is how much the sequence of treatment matters. People often reach for melatonin or caffeine as a first fix without addressing light exposure or schedule consistency, and then conclude “nothing works” when the supplement doesn’t solve a problem it was never positioned to solve alone. The AASM’s own guideline treats most interventions as conditional recommendations, not universal fixes, precisely because shift work sleep disorder responds to layered, individualized strategies rather than a single silver bullet.
The other underappreciated point: this isn’t just a sleep problem. The cardiometabolic and mental health risks tied to chronic circadian disruption mean that treating shift work sleep disorder early is a genuine health investment, not just a comfort issue. If you’ve been telling yourself that the daytime exhaustion and 3 a.m. brain fog are just part of the job, it’s worth reconsidering that assumption with a clinician who can look at your full picture, not just your sleep schedule in isolation.
— Kristofer
Getting Clinical Support for Shift Work Sleep Disorder
If schedule adjustments, light management, and timed melatonin haven’t resolved your symptoms after several weeks, a psychiatric evaluation can identify what’s driving the persistent insomnia or sleepiness, whether that’s the shift work itself, an underlying mood disorder, or both. Imindmental offers telehealth-first psychiatry and medication management built specifically around the reality that people working nontraditional hours can’t always make a 9-to-5 appointment window.
Your first visit typically covers your full shift history, sleep patterns, and any medications or supplements you’re already using, so bring a sleep diary if you’ve been keeping one, even a rough one helps. From there, your provider can discuss appropriate options, from behavioral strategies to medication, tailored to your actual schedule rather than a generic sleep plan. Appointments across Port St. Lucie, Vero Beach, and Stuart, FL are available in person or by telehealth, and booking online takes just a few minutes to get started.
Sources
For deeper reading beyond this guide, the AASM’s 2025 clinical practice guideline offers the current evidence-graded treatment recommendations. The PMC review on shift work and SWSD covers the physiological definition in more depth, and the Cleveland Clinic’s patient guide breaks down symptoms and treatment in plain language for anyone sharing this information with family or coworkers.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
- Extrinsic CRSWD CPG (AASM) – May 2025
- Shift Work and Shift Work Sleep Disorder – PMC – NIH
- Shift Work Sleep Disorder (SWSD): Symptoms & Treatment – Cleveland Clinic

