

Spravato (esketamine) is an FDA-approved, clinic-administered nasal spray for adults with treatment-resistant depression or acute suicidal thoughts, and it can ease symptoms within hours to days. It’s not a take-home medication. You’ll need a documented history of at least two unsuccessful antidepressant trials, a provider evaluation, and supervised dosing at a certified clinic under strict federal monitoring rules.
TL;DR:
- Esketamine significantly improves remission rates when added to oral antidepressants, with about 27% of patients responding by week 8, compared to 17.6%.
- The medication requires strict clinic supervision under REMS regulation, with no take-home doses, and patients must arrange transportation after each visit.
- Most patients experience temporary dissociation and blood pressure spikes during administration, which clinics monitor and manage carefully within observation windows.
- Response to esketamine varies, showing noticeable effects as early as day 2 but typically requires four to eight weeks to evaluate overall effectiveness.
- Proper candidate screening involves confirming previous antidepressant failures, screening for contraindications, and ensuring logistical readiness for in-clinic administration.
Table of Contents
- What Spravato for Depression Actually Treats
- How Esketamine For Depression Works So Quickly
- Does Spravato Actually Work? What The Trials Show
- Spravato Dosage Guidelines And REMS Requirements
- Spravato Side Effects And How Clinics Manage Them
- What A Spravato Treatment Visit Looks Like
- What Spravato Costs And How Insurance Coverage Works
- Where Spravato Fits Alongside Other Depression Treatments
- How Imindmental Delivers REMS-Certified Spravato Care
- The Real Gap In How Spravato Gets Discussed
- Get Evaluated For Spravato Treatment At Imindmental
- Sources
What Spravato for Depression Actually Treats
Spravato is the brand name for esketamine, a nasal spray chemically related to ketamine but refined and dosed specifically for psychiatric use. It works differently from the antidepressants you’ve likely already tried, which is exactly why the FDA carved out a narrow, specific lane for it.
The FDA has approved Spravato for two distinct situations. The first is treatment-resistant depression (TRD) in adults, used alongside an oral antidepressant. The second is depressive symptoms in adults with major depressive disorder who are experiencing acute suicidal ideation or behavior. These are separate indications with separate dosing schedules, and your clinician will determine which one applies to you.
In practice, TRD means you’ve failed to respond adequately to at least two different oral antidepressants during your current depressive episode. That’s the working definition most prescribers use, though every case gets individualized review rather than a checkbox exercise.
Before prescribing, a clinician typically works through several practical checks:
- Confirms prior antidepressant trials were adequate in dose and duration, not just attempted briefly
- Screens for uncontrolled hypertension or cardiovascular disease, since esketamine can raise blood pressure
- Reviews history of psychosis or dissociative disorders, which are typically contraindications
- Assesses substance use history, given esketamine’s abuse potential
- Confirms you have reliable transportation home, since driving after a dose is not permitted
- Discusses pregnancy status and current medications for interaction risks
If you’ve cycled through SSRIs, SNRIs, or augmentation strategies without relief, this is worth raising directly with your psychiatric provider. Spravato treatment eligibility often becomes clearer once your full medication history is on the table.
How Esketamine For Depression Works So Quickly
Most antidepressants you’ve tried work on serotonin, norepinephrine, or dopamine, gradually adjusting monoamine levels over weeks. Esketamine takes a different route entirely. It blocks NMDA receptors in the brain, and that blockade appears to trigger a cascade that promotes synaptic plasticity, essentially helping neurons rebuild connections that depression seems to erode.
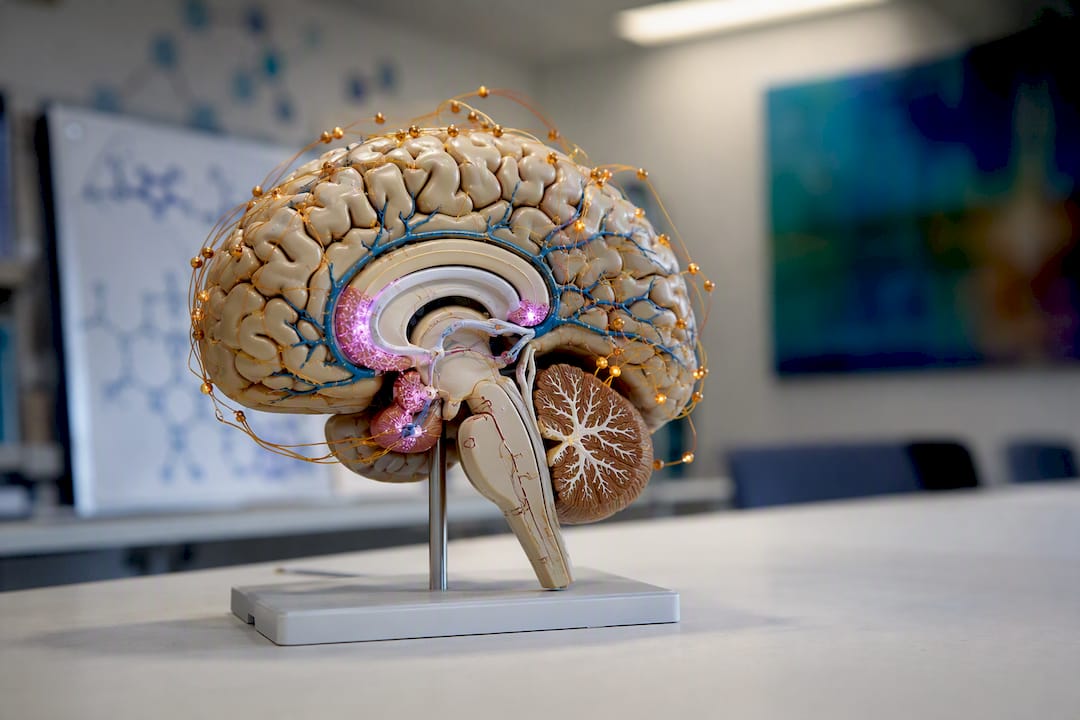
That mechanistic difference explains the timeline difference. Standard antidepressants typically need four to six weeks before you’d notice meaningful change. Esketamine can produce measurable symptom reduction within hours for some patients, with continued improvement over the following days. Johns Hopkins Medicine describes this rapid effect as something that can show up within hours, not weeks, for certain patients.
It’s worth being precise about what “rapid” means here. It doesn’t mean depression vanishes after one dose. It means some patients notice their mood lifting, their thinking clearing, or their suicidal thoughts easing faster than they would on an oral antidepressant alone. The research into exactly why this happens neurologically is still evolving, and response varies significantly from person to person.
Pro Tip: Spravato is almost never prescribed as a standalone treatment. Clinicians typically keep you on your oral antidepressant and often continue or start talk therapy alongside it. Think of Spravato as opening a window rather than replacing the rest of your treatment plan.
Clinically, this combination approach matters. Esketamine seems to work best when it’s given room to interact with ongoing treatment rather than substituting for it. Some psychiatric teams use the treatment period itself, when you’re most receptive, to reinforce coping strategies or process therapeutic material. That’s part of why continuity with your existing provider tends to produce better outcomes than treating Spravato as an isolated intervention.
Does Spravato Actually Work? What The Trials Show
The honest answer is: it works meaningfully better than placebo for a meaningful share of patients, though not universally and not permanently without maintenance.
A 2026 meta-analysis pooling esketamine trials found that adding esketamine to an oral antidepressant produced a remission risk ratio of 1.52 compared with oral antidepressant alone at four weeks, with a 95% confidence interval of 1.20 to 1.92.
By the numbers: Esketamine plus an antidepressant produced remission in 27.1% of patients by week 8 in a major head-to-head trial, compared with 17.6% on an alternative augmentation strategy, with the advantage holding through week 32.
That figure comes from the ESCAPE-TRD trial, published in the New England Journal of Medicine, which directly compared esketamine plus an SSRI or SNRI against quetiapine plus an SSRI or SNRI. Esketamine’s group also showed a lower relapse rate through week 32, suggesting the benefit isn’t purely a short-lived spike.
What does this mean if you’re the one considering treatment? It means response isn’t guaranteed, but the odds tilt meaningfully in your favor compared with staying on an oral antidepressant alone or switching to certain other augmentation strategies. Early signals often show up by day 2, with a fuller picture emerging by week 4 and week 8. If you’re not responding by the four-week mark, your provider will typically reassess rather than continue indefinitely.

The limitation worth naming honestly: most trial populations were adults without severe cardiovascular disease or active substance use disorder, so results may not translate directly to every patient profile. Long-term maintenance data continues to accumulate, and individual response still varies considerably. For a deeper look at how these numbers translate into real-world outcomes, Imindmental’s breakdown of Spravato success rates walks through the evidence in more detail.
Spravato Dosage Guidelines And REMS Requirements
Dosing depends entirely on which indication you’re being treated for, and neither schedule is something you’ll manage at home.
For treatment-resistant depression, the typical induction schedule is 56 mg or 84 mg twice weekly for the first four weeks. After that, most patients transition to once-weekly dosing for weeks five through eight, then to a maintenance schedule of once weekly or every other week, based on how you’re responding. For MDD with acute suicidal ideation or behavior, the regimen is generally 84 mg twice weekly for four weeks, with reassessment at that point.
A typical administration visit follows this sequence:
- You check in and staff record baseline vitals, including blood pressure and heart rate.
- You self-administer the nasal spray under direct staff supervision, using multiple device sprays spaced five minutes apart to reach your full dose.
- Staff monitor you continuously for roughly two hours, tracking blood pressure, sedation level, and oxygen saturation.
- Around the 40-minute mark, according to Mayo Clinic, dissociative effects and sedation tend to peak, so this window gets the closest attention.
- Once vitals stabilize and dissociation resolves, staff use standard discharge criteria to clear you to leave, but only with a ride arranged in advance.
This entire process exists because of the Risk Evaluation and Mitigation Strategy, or REMS, a federal safety program the FDA requires for Spravato specifically because of its dissociative and sedative effects and abuse potential.
REMS requirements shape nearly everything about how the drug reaches you:
- Only REMS-certified clinics can dispense and administer Spravato, and the medication ships directly to the certified site, never to your home.
- No take-home doses are permitted under any circumstance.
- You must be monitored on-site for the full observation window after every single dose.
- The clinic must document your blood pressure, sedation status, and dissociation resolution before discharge.
- You cannot drive yourself home; transportation must be arranged before your appointment.
That last point trips up more patients than any other logistical detail. Plan your ride the same way you’d plan for a procedure requiring sedation, because functionally, that’s what this is.
Spravato Side Effects And How Clinics Manage Them
The side effect profile is well documented, and most of it is expected, monitored, and temporary rather than alarming.
Dissociation, meaning perceptual changes like feeling detached from your body or surroundings, occurs in a wide range of patients. Clinical trial data cited in the prescribing information put dissociative symptoms at 61% to 84% of treated patients, with sedation affecting 48% to 61%. Both effects typically peak around 40 minutes post-dose and resolve within the two-hour observation window.
Roughly 4.6% of patients on active esketamine discontinued treatment due to adverse reactions, compared with 1.4% on placebo, according to pooled trial data in the drug’s label.
Beyond dissociation and sedation, clinics watch closely for:
- Blood pressure spikes. Esketamine can transiently raise blood pressure, so clinics check it before dosing, near the 40-minute peak, and before discharge. If readings exceed a clinic’s threshold, staff may delay dosing or hold the next dose until it’s controlled.
- Respiratory depression or loss of consciousness. These are rare but serious, which is exactly why REMS mandates on-site monitoring rather than home use.
- Abuse and diversion risk. Because esketamine is a Schedule III controlled substance related to ketamine, clinicians screen for substance use disorder history before starting treatment and monitor for signs of misuse throughout.
If a patient develops concerning symptoms during the observation window, staff typically extend monitoring time rather than discharge on schedule. This is standard practice, not a red flag about your specific treatment. It’s exactly why the two-hour window exists in the first place.
What A Spravato Treatment Visit Looks Like
Knowing what happens before you walk in makes the actual visit far less intimidating.
- Before your appointment, you’ll complete intake paperwork covering your medication list, recent vitals, and informed consent documentation. Some clinics handle parts of this through telehealth ahead of time.
- On arrival, staff record baseline blood pressure and pulse, and confirm you haven’t eaten a large meal recently, since nausea can occur.
- During dosing, you self-administer under supervision, spacing device sprays five minutes apart until you reach your prescribed dose.
- During the observation period, which typically runs two to three hours total including check-in and discharge, staff monitor vitals and check in on dissociation and sedation levels at intervals.
- At discharge, you’re cleared once vitals are stable and dissociative effects have resolved, and you leave with the companion or ride you arranged beforehand.
Plan to treat the whole visit as a two-to-three-hour commitment, not a quick appointment. Bring a driver, skip driving yourself for the rest of the day, and avoid scheduling anything demanding immediately afterward. Imindmental’s guide to Spravato treatment in Stuart, FL walks through this same logistics pattern in more local detail.
What Spravato Costs And How Insurance Coverage Works
Cost breaks down into several separate pieces: the medication itself, a facility or administration fee for the monitored visit, and the provider evaluation fee. None of these are flat, standardized numbers, since they depend on your clinic, your insurance plan, and your specific dosing schedule.
Insurance coverage for Spravato has become more common since its FDA approval, but prior authorization is standard practice at nearly every clinic. That means your insurer will typically want documentation of your prior antidepressant failures before approving coverage, which is one more reason a thorough medication history matters early in the process.
A few practical steps make this smoother:
- Call your insurance benefits line before scheduling and ask specifically about esketamine or Spravato coverage and prior authorization requirements.
- Ask your prescribing clinic whether they handle prior authorization paperwork on your behalf, since many do.
- Look into manufacturer patient support programs, which sometimes offer copay assistance for eligible patients.
- Confirm the clinic is REMS-certified before booking, since only certified sites can legally dispense the drug. You can ask directly, or check with the clinic’s front desk staff.
If cost is a barrier, raise it directly with your care team. Many practices have a process for working through coverage gaps rather than leaving patients to figure it out alone.
Where Spravato Fits Alongside Other Depression Treatments
Spravato isn’t designed to replace your broader treatment plan. It’s approved as an addition to an oral antidepressant for TRD, and it’s most effective when your care team treats it as one piece of a larger strategy rather than a fix on its own.
Compared with other advanced options, the differences are structural as much as clinical:
- Transcranial Magnetic Stimulation (TMS) uses magnetic pulses to stimulate specific brain regions over daily sessions across several weeks, with no dissociative effects and no monitoring requirement afterward.
- Electroconvulsive therapy (ECT) involves brief controlled seizures under anesthesia, typically reserved for more severe or urgent presentations, and requires more intensive logistics than Spravato.
- Spravato sits between these in intensity, twice-weekly visits during induction, in-clinic dosing, and a shorter but more frequent monitoring requirement than TMS.
Which approach a clinician recommends depends on your specific history, how urgently symptoms need addressing, and what you’ve already tried. Psychotherapy and medication management typically continue throughout, regardless of which advanced treatment you pursue. If oral medications haven’t worked and you’re weighing next steps, Imindmental’s guide on what to do when depression medication isn’t working covers the decision points in more depth, and the MindShift Psychological Center offers a useful overview of how therapy strategies fit alongside medical treatments like these.
How Imindmental Delivers REMS-Certified Spravato Care
Imindmental operates as a REMS-certified Spravato provider across three Florida locations: Port St. Lucie, Vero Beach, and Stuart. That certification isn’t optional paperwork. It’s the federal requirement that allows a clinic to legally dispense and supervise this medication at all.

Care at Imindmental follows an integrated model rather than a standalone procedure. Psychiatry and therapy typically continue alongside Spravato treatment, and many patients start the process through telehealth intake before their first in-person dosing visit. The team also handles insurance verification ahead of scheduling, so you’re not left guessing about coverage on the day of your appointment.
Here’s what that integrated approach typically includes:
- A psychiatric evaluation to confirm eligibility and review your prior antidepressant history
- Telehealth intake options to start the process without an initial in-person visit
- Insurance benefit verification before your first dosing session
- Coordinated therapy and medication management alongside your Spravato schedule
If you’re wondering whether you qualify, the most direct next step is a formal evaluation rather than self-diagnosis. Details on eligibility and the full Spravato treatment program are available directly through Imindmental’s care team.
The Real Gap In How Spravato Gets Discussed
Most coverage of Spravato swings between two extremes: breathless “miracle treatment” framing or dry regulatory summaries that leave out what the experience actually feels like. Neither serves the person deciding whether to pursue it.
The evidence genuinely supports Spravato as a meaningfully better option than continuing to cycle through oral antidepressants alone for treatment-resistant depression, particularly for patients already carrying acute suicidal thoughts. A 52% higher likelihood of remission at four weeks, per the Frontiers meta-analysis, is not a marginal signal. But the conventional advice online tends to undersell the logistics: the two-hour visits, the twice-weekly commitment during induction, the transportation requirement. Those details determine whether treatment is realistic for your life, not just whether the drug works biologically.
What I’d prioritize first, if I were in your position, isn’t the mechanism or the statistics. It’s finding a psychiatric provider who will walk through your full medication history honestly and tell you plainly whether you meet the treatment-resistant definition. The science is solid. The logistics are where most people get blindsided.
— Kristofer
Get Evaluated For Spravato Treatment At Imindmental
If you’ve tried two or more antidepressants without lasting relief, a psychiatric evaluation, not another medication switch, is usually the most useful next step. Imindmental offers exactly that: a REMS-certified Spravato program built into a broader psychiatry and therapy practice across Port St. Lucie, Vero Beach, and Stuart, so you’re not managing this treatment in isolation from the rest of your care.
What sets this apart from piecing together separate providers is coordination. Your psychiatric evaluation, insurance verification, and dosing schedule all run through one connected team, rather than bouncing between a prescriber and a separate infusion or nasal spray clinic. Telehealth intake makes starting the conversation easier, especially if scheduling an in-person visit feels like one more barrier on top of an already exhausting search for relief.
The most useful thing you can do this week is book a psychiatric evaluation to review your treatment history and find out directly whether Spravato is a fit for you.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Frontiers in Psychiatry — 2026 meta-analysis on esketamine
- DailyMed — SPRAVATO prescribing information
- Mayo Clinic — Esketamine overview
- Johns Hopkins Medicine — Esketamine for treatment-resistant depression

