

SPRAVATO is available only through the SPRAVATO REMS, a restricted distribution program set by the FDA. Certified healthcare settings, pharmacies, and prescribers must enroll, outpatients must be enrolled individually, and every dose must be self-administered under direct observation followed by at least two hours of monitoring, including pulse oximetry, with a monitoring form submitted afterward.
TL;DR:
- Healthcare settings and pharmacies must complete separate enrollment and staff training before they can order or dispense SPRAVATO, with all documentation kept on file for audits.
- Every outpatient dose requires direct observation, a strict two-hour monitoring period, and detailed documentation of vital signs and symptoms to ensure safety.
- Patients must complete enrollment and safety forms prior to treatment, and no medication can be taken home; proper discharge criteria are essential for safe release.
- Clinics with staff turnover should regularly review and update training, shipment logs, and monitoring records to stay compliant and avoid common audit findings.
- Transferring patients between certified sites requires verified enrollment and documentation confirmation through official REMS channels before treatment continues.
Table of Contents
- What the SPRAVATO REMS is and why it exists
- Who must enroll and be certified under SPRAVATO REMS requirements
- How a clinic or pharmacy completes SPRAVATO REMS certification
- Administration and monitoring: what a compliant SPRAVATO session looks like
- Documentation, monitoring forms, and reporting timelines
- Safety, contraindications, and a concise dosing overview
- Clinic responsibilities for audits, recordkeeping, and staying compliant
- Enrolling and transferring patients between certified sites
- iMind clinician perspective: running REMS workflow in a Florida clinic
- Getting Spravato treatment through a REMS-certified provider in Florida
- Sources
What the SPRAVATO REMS is and why it exists
A REMS, or Risk Evaluation and Mitigation Strategy, is a safety program the FDA requires when a drug’s benefits only outweigh its risks if providers follow specific conditions of use. SPRAVATO carries a boxed warning covering sedation, dissociation, respiratory depression, and potential for abuse or misuse, and esketamine’s chemical relationship to ketamine is part of why regulators wanted guardrails around who can prescribe, dispense, and administer it.
The REMS does not exist to slow down access for its own sake. It exists because SPRAVATO’s risk profile changes depending on the minutes right after dosing, not the drug’s long-term safety record. That is a distinction worth sitting with: this is a program built around a narrow, predictable window of risk, not a blanket restriction on the medication itself.
The REMS accomplishes this by requiring:
- Certification of every healthcare setting, pharmacy, and prescriber before SPRAVATO can be ordered, dispensed, or administered
- Direct observation of every dose, with no take-home prescriptions permitted
- A minimum two-hour monitoring period after each dose
- Submission of monitoring documentation for every outpatient treatment session
Who must enroll and be certified under SPRAVATO REMS requirements
Four distinct parties fall under the REMS umbrella, and each has a different enrollment path. Understanding which category your clinic or pharmacy fits into determines which forms you file and how quickly you can start treating patients.
Outpatient healthcare settings carry the heaviest enrollment burden. Each site must complete a Healthcare Setting Enrollment Form, designate an Authorized Representative who takes responsibility for REMS compliance, and confirm that staff training has been completed before ordering any SPRAVATO product.
Inpatient settings get a narrower path in some cases, since hospital pharmacies operating within a single certified facility may qualify under simplified enrollment rules tied to that facility’s existing certification. Pharmacies, whether hospital-based or outpatient, must enroll separately and can only dispense SPRAVATO to certified healthcare settings, never directly to a patient for home use.
Prescribers must be certified through their affiliated healthcare setting and need to be physically present or immediately available during administration. Patients enrolling for outpatient treatment need their own Patient Enrollment Form completed before their first dose, confirming they understand the monitoring and transportation requirements ahead.
- Healthcare settings: enroll the facility, name an Authorized Representative, document staff training
- Pharmacies: enroll separately, dispense only to certified sites, never to patients directly
- Prescribers: certify through the healthcare setting, remain available during dosing
- Patients (outpatient): complete enrollment before the first administered dose
How a clinic or pharmacy completes SPRAVATO REMS certification
Getting a new clinic or pharmacy certified is a linear process, and skipping a step is the most common reason practices get stuck waiting on their first shipment.
- Designate an Authorized Representative. This person becomes the point of accountability for REMS compliance at your site and typically coordinates training, documentation, and audit response going forward.
- Complete staff training. Every provider and support staff member involved in ordering, dispensing, or monitoring needs documented training completion, kept on file for audit purposes.
- Review REMS materials. Pull the current prescribing information, Medication Guide, and Instructions for Use so your clinical team is working from the same source document.
- Submit the correct enrollment form. Healthcare settings and pharmacies each file separate forms at SPRAVATOrems.com, then wait for a certification confirmation notice before placing any order.
- Set up ordering and verification logistics. Once certified, confirm your pharmacy relationship, establish a reorder cadence, and build an onboarding checklist for new staff so training records don’t lapse when someone new joins the team.
Pro Tip: Print your certification confirmation notice and file it alongside your Authorized Representative documentation. Auditors ask for this pairing more often than any other single document, and having it ready saves a scramble later.
Administration and monitoring: what a compliant SPRAVATO session looks like
The dosing room is where REMS requirements become concrete. A patient never takes SPRAVATO home. Instead, they self-administer the nasal spray while a provider observes directly, confirming the device is used correctly and that the full dose is delivered.
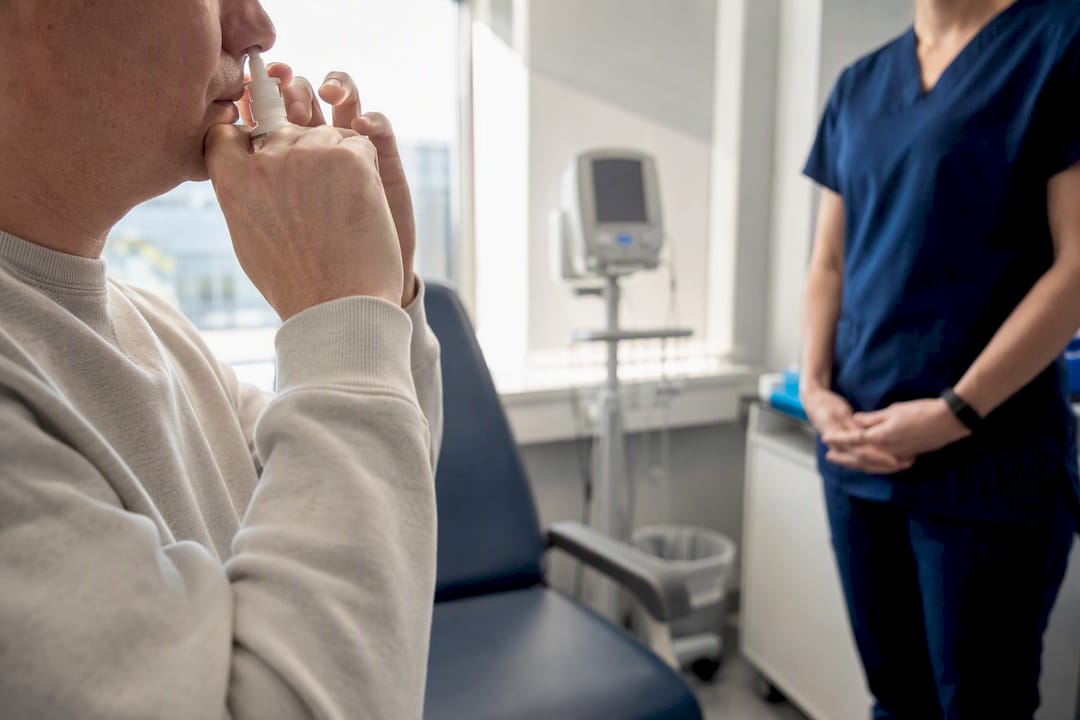
From that point, the clock starts on a minimum two-hour monitoring window, and this is not a flexible guideline. Pulse oximetry runs throughout, alongside periodic blood pressure and heart rate checks, because respiratory depression and blood pressure changes are among the risks the REMS was built to catch early.
Providers watch for sedation, dissociative symptoms, and any shift in vital signs outside the patient’s baseline, documenting observations at intervals rather than waiting until the end of the session to write everything down. A patient who seems unusually drowsy at the ninety-minute mark needs that noted in real time, not summarized after the fact.
Two hours, every time. Regardless of how many prior sessions a patient has completed without incident, each dose requires its own full monitoring period. Clinical stability on session ten does not shorten the requirement on session eleven.
Discharge criteria matter as much as the monitoring itself. A patient needs to demonstrate they’ve returned to their baseline level of alertness, orientation, and blood pressure before leaving. Key documentation points during a session include:
- Time of dose administration and monitoring start
- Pulse oximetry readings at regular intervals
- Blood pressure and heart rate checks
- Any dissociative or sedative symptoms observed, with timestamps
- Clinical judgment supporting the discharge decision
If a patient shows signs of significant respiratory depression or a severe dissociative reaction, clinics need an emergency response protocol ready, including immediate escalation to emergency services if vital signs don’t stabilize with supportive care.
Documentation, monitoring forms, and reporting timelines
Paperwork is not an afterthought in the SPRAVATO REMS. It is the mechanism the program uses to prove, after the fact, that every requirement was actually followed.
- Patient Enrollment Form. Complete this before the patient’s first outpatient treatment session. The healthcare setting typically handles submission, and treatment shouldn’t begin until enrollment is confirmed.
- Patient Monitoring Form. Complete this after every single outpatient session, not just the first, and submit it within 7 days. The form captures dose, lot number, monitoring duration, pulse oximetry results, and any adverse symptoms observed.
- Recordkeeping. Keep lot numbers, dosing records, staff training completions, and shipment logs organized and retrievable, since these are the first documents an auditor will request.
- Serious Adverse Event reporting. Document and report SAEs according to the reporting pathway outlined in the prescribing information, separate from the routine monitoring form submission.
Safety, contraindications, and a concise dosing overview
Clinicians counseling patients need the essentials at hand without re-reading the full prescribing information at every visit, though the complete label remains the authoritative source for edge cases.
The boxed warning covers sedation, dissociation, respiratory depression, and abuse potential, and contraindications generally include a history of hypersensitivity to esketamine or ketamine. Full contraindication and warning details belong in the current package insert, not summarized secondhand.
Dosing follows an induction and maintenance structure. For treatment-resistant depression and for major depressive disorder with suicidal ideation, common regimens use 56 mg or 84 mg dosed twice weekly during induction, then taper to weekly or every-other-week maintenance dosing based on how the patient responds and tolerates treatment.
Co-administration with benzodiazepines or opioids raises the stakes on monitoring, since combined sedative effects can intensify respiratory depression risk. Patients on either class of medication may need closer observation during their monitoring window.
- Confirm no driving and no operating hazardous equipment until after a full night’s restful sleep
- Arrange transportation home before the appointment, not after
- Flag any benzodiazepine or opioid use during intake screening
- Review sleep and next-day plans with the patient before discharge
Pro Tip: Ask patients to name their ride home before scheduling the appointment, not on the day of treatment. Clinics that build transportation confirmation into intake reduce same-day scheduling conflicts significantly.
Clinic responsibilities for audits, recordkeeping, and staying compliant

REMS compliance is not a one-time certification event. Janssen and third-party auditors can request documentation at any point, and clinics that treat certification as a finish line rather than an ongoing responsibility are the ones that struggle when that request arrives.
Maintain training records for every staff member involved in SPRAVATO ordering, dispensing, or monitoring, along with current Authorized Representative documentation. Reconcile shipment and dispensing logs against actual patient dose records on a regular schedule rather than waiting for an audit to surface a discrepancy.
- Run periodic internal reviews to catch missing monitoring forms before the 7 day deadline slips
- Confirm training records are current whenever staff turnover occurs
- Cross check shipment logs against dispensing records monthly
- Address gaps immediately rather than batching corrections
The most common audit findings tend to be simple: a monitoring form submitted late, a training record that lapsed after a staff change, or a shipment log that doesn’t quite match dispensing totals. Catching these internally, before an external audit does, is the difference between a quick correction and a compliance headache.
Enrolling and transferring patients between certified sites
Patients occasionally need to move between certified locations, whether due to relocation, insurance changes, or simply switching providers. The process is straightforward as long as each step happens in order.
- Complete the Patient Enrollment Form at the patient’s first outpatient session, with the healthcare setting handling submission and confirming enrollment before any dose is scheduled.
- Verify enrollment status before scheduling or dispensing, since treatment shouldn’t proceed on the assumption that paperwork “probably went through.”
- Document the transfer when a patient moves between certified settings, notifying the REMS program as needed so records stay accurate across sites.
- Use official REMS contacts for verification questions. The REMS support line and portal can confirm a site’s certification status directly.
iMind clinician perspective: running REMS workflow in a Florida clinic
Compliance works best when it is boring in the good way: the same intake sequence, the same monitoring checklist, the same discharge criteria, every single time. Our workflow at iMind Mental Health Solutions leans on telehealth for pre-screening and insurance verification, so the in-person visit is reserved entirely for dosing and observation rather than paperwork.
We built standardized monitoring templates specifically because handwritten notes under time pressure are where documentation errors creep in. A checklist that prompts staff at the fifteen-minute, sixty-minute, and two-hour marks catches what memory alone won’t.
— Kristofer
Getting Spravato treatment through a REMS-certified provider in Florida
Imindmental operates REMS-compliant Spravato treatment at locations in Port St. Lucie, Vero Beach, and Stuart, giving Florida patients a certified path to esketamine therapy without having to navigate certification questions themselves.
If you’re considering Spravato, verifying certification is simple: ask any prospective provider whether they’re enrolled in the SPRAVATO REMS as a certified healthcare setting, and bring a list of current medications so staff can screen for interactions like benzodiazepines or opioids before your first session. Patients local to the Treasure Coast can review what to expect on the Spravato treatment page for Port St. Lucie or the Stuart location’s guide before booking.
Ready to take the next step? Visit the Spravato treatment center page to review eligibility and schedule an initial evaluation with a certified provider.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- DailyMed – SPRAVATO (esketamine) hydrochloride solution
- SPRAVATO® REMS Program Overview (REMSProgramOverview.pdf)
- Dosing of SPRAVATO – Post Administration Monitoring (Janssen Medical Connect)

