

Most people who complete a standard TMS course begin noticing early signals of improvement within the first one to two weeks, with clearer, more meaningful symptom relief typically emerging between weeks four and six. A full acute course usually runs 30–36 sessions, delivered five days a week over four to six weeks, though accelerated protocols can compress that calendar significantly. The most important number to track is not the week on the calendar but the cumulative sessions delivered, because registry evidence ties session count directly to outcomes.
Here is what to expect at each stage:
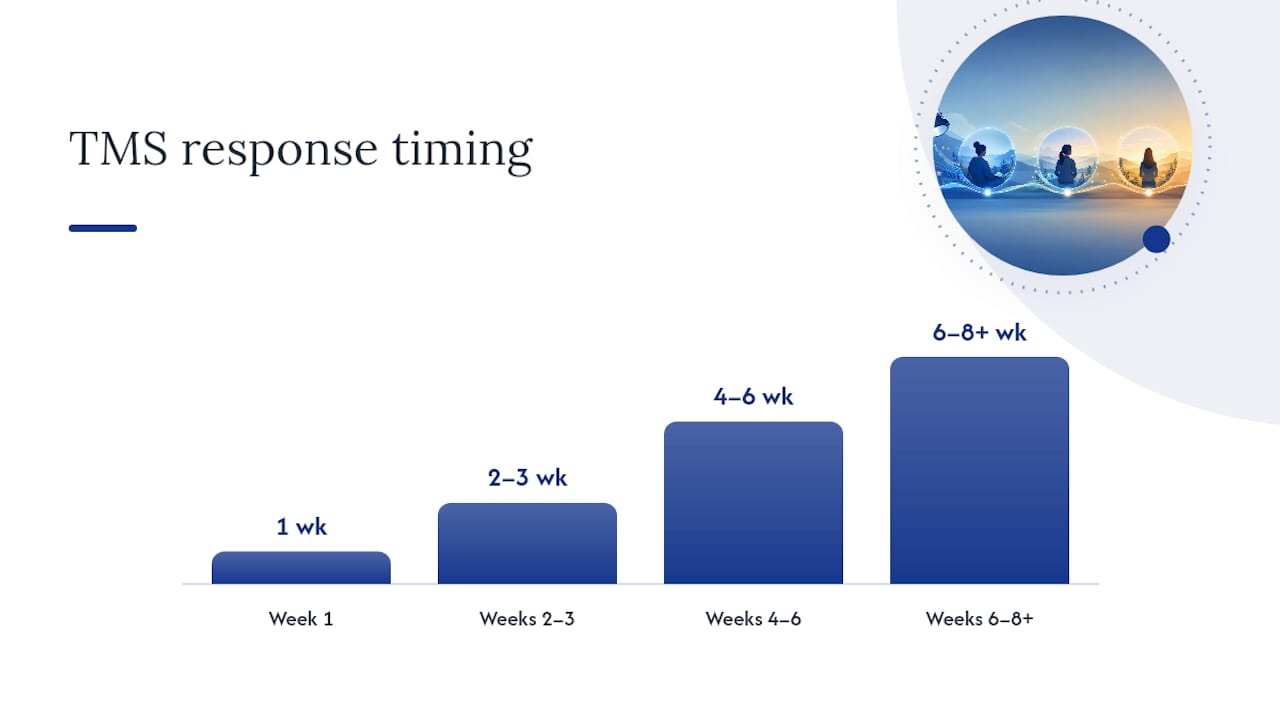
- Earliest signals (weeks 1–2): Subtle shifts in sleep quality, energy, or irritability, not yet a full mood lift
- Partial response (weeks 2–3): Clinicians begin documenting PHQ-9 trends; some patients notice a steadier baseline
- Clearer improvement (weeks 4–6): The window when most patients and clinicians see meaningful symptom change
- Extended courses (weeks 6–8+): Considered when response is slower or when the planned session count has not yet been reached
- Measurement: Ask your clinician to review your PHQ-9 score at each reassessment visit so you have an objective marker alongside how you feel
Before your first session, ask your clinician two things: how many total sessions are planned, and at which session count they will conduct a formal reassessment.
Key Takeaways
A standard TMS course runs 30–36 sessions over four to six weeks, and registry evidence from 13,732 patients confirms that completing the full planned course, particularly reaching 36 sessions, is associated with the best outcomes.
| Point | Details |
|---|---|
| Typical course length | 30–36 sessions, five days per week, over four to six weeks for standard rTMS |
| When improvement usually appears | Early signals often emerge in weeks 1–2; clearer benefit is most common between weeks 4–6 |
| Session count matters most | Registry data show fewer than 30 sessions is associated with inferior PHQ-9 outcomes; don’t stop early |
| Measure progress objectively | Ask your clinician for your PHQ-9 score at each reassessment to track change alongside how you feel |
| Imindmental TMS services | Imindmental offers TMS at Port St. Lucie, Vero Beach, and Stuart, FL, with insurance verification before your first session |
Table of Contents
- What does the TMS treatment timeline look like across different protocols?
- What should you expect week by week during TMS therapy?
- How do clinicians measure your response, and what does the evidence show?
- Which personal and protocol factors change how quickly you’ll notice improvement?
- What should you do if you’re not improving on schedule?
- What side effects should you expect, and when is it urgent?
- How much does TMS cost, and how do you plan the logistics?
- What does the largest TMS registry study tell us about session counts?
- A clinical perspective on setting realistic TMS expectations
- TMS therapy is available at Imindmental in Port St. Lucie, Vero Beach, and Stuart, FL
- Sources
What does the TMS treatment timeline look like across different protocols?
Not every TMS course follows the same calendar, and understanding why helps you plan your schedule and set realistic expectations. The protocol your clinician recommends determines how many times per day you come in, how long each visit lasts, and how many total weeks the course spans.
Session durations vary by protocol, ranging from roughly 3 minutes up to about 37 minutes, which patients may find varies widely. Your first appointment will run longer than any follow-up because coil placement and dosing are established that day, a process sometimes called motor threshold mapping.
Accelerated programs deliver multiple brief sessions per day, which can shorten the total calendar time considerably. VA guidance confirms that protocol frequency can shift the calendar from roughly one week up to six to eight weeks depending on total sessions delivered and how many are given per day.

Pro Tip: Ask your clinic for the exact protocol name before your first appointment. Knowing whether you are on standard rTMS, theta-burst, or an accelerated schedule tells you immediately how to block your work calendar and arrange transportation.
What should you expect week by week during TMS therapy?
One of the most common sources of anxiety during TMS is not knowing whether what you are experiencing is normal. The week-by-week picture below reflects what clinical practice and published evidence describe as common trajectories, though individual responses vary.
Week 1
The first week is largely about tolerating the procedure and letting cumulative stimulation begin. Some patients notice subtle changes in sleep quality or energy before any mood shift appears. These early signals are encouraging but not predictive on their own; some patients who eventually respond strongly notice nothing in week one.
Weeks 2–3
Partial responses often become visible here. Clinicians typically document PHQ-9 scores at this stage to establish a trend line. You might notice that your worst hours of the day are slightly less intense, or that you are engaging a little more with daily activities. This is also when some patients feel frustrated that the change feels small. That frustration is understandable, and it is worth discussing with your clinician rather than interpreting it as treatment failure.
Weeks 4–6
This is the window that Mayo Clinic and most clinical guidelines identify as the period when symptom relief commonly becomes noticeable. Many patients describe this as the point where the cumulative effect of 20 or more sessions starts to feel qualitatively different. For those on a standard 30–36 session course, this window often coincides with the final stretch of the acute course.
Weeks 6–8+
Slower responders are not treatment failures. Some patients follow a delayed trajectory, and registry data suggest that extending the course beyond 36 sessions can produce continued improvement without evidence of a plateau. Extended courses are a clinical decision, not a sign that something went wrong.
When to contact your clinician between visits:
- Sudden worsening of mood or emergence of new symptoms
- Severe headache or scalp pain that does not resolve within a few hours after a session
- Any new neurological symptom (unusual sensations, vision changes, weakness)
- Feeling that sessions have stopped producing any effect after week four
How do clinicians measure your response, and what does the evidence show?
The PHQ-9 (Patient Health Questionnaire-9) is the most widely used validated scale for tracking depression severity during TMS. It is a nine-item self-report tool scored from 0 to 27, and clinicians use it at regular intervals to document whether you are responding or remitting. A remitter reaches a score of 4 or below, indicating minimal symptoms.
Clinical and trial literature confirms that PHQ-9 and other validated scales are the standard measurement tools across TMS studies and centers, though protocols and session counts vary considerably between settings. This variability is one reason why a single “expected response rate” is difficult to state with precision.
Registry evidence from a sample of 13,732 patients found that courses with fewer than 30 sessions were associated with inferior endpoint PHQ-9 outcomes, while the group completing 36 sessions showed the greatest PHQ-9 reduction at endpoint. Extending beyond 36 sessions was associated with further improvement without evidence of a plateau.
Source: Dosing TMS in major depressive disorder — PubMed registry analysis
That finding carries a practical implication: if you are at session 20 and feeling uncertain, the data support continuing to the planned endpoint rather than stopping early. Clinician judgment remains central, but objective PHQ-9 trends give both you and your provider a shared, measurable reference point.
Which personal and protocol factors change how quickly you’ll notice improvement?
Your individual TMS treatment duration is shaped by factors on both sides of the equation: who you are as a patient, and which protocol your clinician selects. Knowing these factors helps you set personalized expectations rather than comparing your progress to someone else’s.
Patient-level factors that tend to affect response speed:
- Treatment resistance history: Patients who have tried multiple antidepressants without adequate relief may respond more slowly or require a longer course
- Comorbid anxiety: Anxiety alongside depression is associated with a somewhat slower or more variable response trajectory in some clinical observations
- Medication changes during the course: Starting, stopping, or adjusting medications mid-course can complicate the timeline and make it harder to attribute changes to TMS alone
- Baseline symptom severity: Higher baseline PHQ-9 scores often mean more room for measurable improvement, but they can also mean a longer path to remission
Protocol-level factors:
- Accelerated schedules (multiple sessions per day) compress the calendar but require more logistical flexibility
- Deep TMS using H-coil technology reaches deeper cortical structures and may have a different onset profile than surface-level rTMS
- Higher total session counts, particularly courses reaching 36 sessions or beyond, are associated with better outcomes in registry data
- Theta-burst stimulation delivers stimulation in shorter bursts and can be administered multiple times per day in specialized settings, altering the calendar without necessarily changing the clinical target
Pro Tip: Before your first session, ask your clinician: “Given my history and the protocol you’re recommending, at what session count should I expect to see a measurable change on the PHQ-9?” That question anchors your expectations to your specific situation, not a generic average.
What should you do if you’re not improving on schedule?
Early nonresponse does not predict final outcome, and this is one of the most clinically important points in the entire TMS therapy process. The registry data cited above make clear that patients who received fewer than 30 sessions had worse outcomes than those who completed 36, which means stopping at session 15 or 20 because you feel uncertain may cost you the response that was still building.
Registry data from 13,732 patients show that completing the full planned course, particularly reaching 30–36 sessions, is associated with meaningfully better outcomes than stopping early.
Source: PubMed registry analysis
Concrete steps if progress feels slow:
- Schedule a formal clinician review and ask for your current PHQ-9 score compared to baseline
- Confirm how many sessions have been delivered and whether the planned total is still on track
- Ask whether any protocol adjustment (pulse pattern, coil position, session frequency) is indicated
- Discuss whether augmentation strategies, such as medication optimization, are appropriate alongside TMS
- If you are combining TMS with therapy, consider whether session frequency or focus needs adjustment
Pro Tip: Bring a written list of specific changes you have or have not noticed since starting. Clinicians can act on “my sleep improved but my motivation hasn’t moved” far more effectively than a general “I don’t think it’s working.”
What side effects should you expect, and when is it urgent?
TMS is generally well tolerated, and most side effects are mild and transient. Understanding what is normal helps you stay calm during the course and recognize the rare situations that require prompt attention.
Common side effects (typically mild and short-lived):
- Scalp discomfort or tingling at the coil site during stimulation
- Headache in the hours following a session, usually resolving with over-the-counter pain relief
- Facial muscle twitching or jaw movement during stimulation, which is normal and stops when the pulse stops
- Fatigue or lightheadedness immediately after a session
Rare but serious risks:
Seizure is the most serious known risk, though it is rare in properly screened patients. Certain metal implants near the head (cochlear implants, aneurysm clips, deep brain stimulators) are contraindications that your clinic will screen for before treatment begins. If you experience a seizure, loss of consciousness, or sudden severe neurological symptoms during or after a session, seek emergency care immediately.
Practical safety steps:
- Disclose all medications, supplements, and implanted devices before your first session
- Plan transportation for your first few sessions until you know how you respond; driving immediately after is generally fine for most patients, but confirm with your clinic
- Ask your clinic specifically about contraindication screening so you know it has been completed
Pro Tip: Keep a brief daily log of how you feel in the hours after each session during the first two weeks. Patterns in that log help your clinician distinguish a normal adjustment response from something worth investigating.
How much does TMS cost, and how do you plan the logistics?
Insurance coverage for TMS has expanded considerably, particularly for treatment-resistant depression. Most major commercial insurers and Medicare cover TMS for major depressive disorder when medical necessity criteria are met, which typically requires documented failure of one or more antidepressant trials. Pre-authorization is almost always required, and the process can take one to three weeks, so starting that paperwork before your first appointment matters.
Out-of-pocket costs vary widely depending on your plan, deductible status, and whether your clinic is in-network. Verifying benefits directly with your insurer before committing to a course is the single most important financial step you can take.
Daily time commitment: Your first intake and mapping appointment will run longer than any subsequent session. Routine follow-up sessions are shorter, though the exact check-in-to-exit time depends on the protocol. Ask your clinic for the expected total time from arrival to departure, not just the stimulation time, so you can plan your workday accurately.
Checklist before your first session:
- Insurance card and pre-authorization confirmation number
- Complete medication list, including supplements and over-the-counter medications
- List of any implanted devices or prior neurosurgical procedures
- Transportation plan for the first week
- Work schedule flexibility for daily morning or afternoon appointments
Pro Tip: Ask your clinic whether they offer early morning or late afternoon slots. A consistent daily time slot is easier to maintain over a six-week course than a rotating schedule, and consistency supports treatment adherence.
What does the largest TMS registry study tell us about session counts?
The most clinically relevant piece of evidence for planning your TMS course comes from a registry analysis of 13,732 patients that examined the relationship between the number of sessions delivered and PHQ-9 outcomes at the end of the acute course. The findings are direct: patients who received fewer than 30 sessions had inferior endpoint outcomes compared to those who completed more. The group that ended at 36 sessions showed the greatest PHQ-9 reduction at endpoint, and extending beyond 36 sessions was associated with continued improvement without evidence of a plateau.
VA guidance reinforces the scheduling dimension: protocol frequency, specifically how many sessions are delivered per day, can shift the total calendar from roughly one week to six to eight weeks while targeting the same clinical goal. That means two patients receiving the same total session count may finish weeks apart depending on whether they are on a standard or accelerated schedule.
The practical implication for you: before your course begins, ask your clinician how many total sessions are planned and under what circumstances that number might be extended. Stopping early because progress feels slow, without reaching at least 30 sessions, is the scenario the registry data most clearly argue against. Discuss planned total sessions with your provider before making any decision to discontinue.
A clinical perspective on setting realistic TMS expectations
Setting a realistic timeline is one of the most meaningful things a clinician can do for a patient starting TMS. The week-by-week framework in this article reflects what the evidence supports, but the most important conversation happens before session one: agreeing on how many sessions are planned, what objective measure you will use to track progress, and at what point you will formally reassess together.
What often gets missed in general TMS information is that the calendar week matters less than the cumulative session count. A patient on an accelerated schedule who finishes 36 sessions in two weeks is in a very different place than one who stops at session 18 after four weeks and concludes the treatment did not work. The registry data make that distinction concrete, not theoretical.
If you are considering TMS and want to understand how your specific history, diagnosis, and protocol choice will shape your personal timeline, the right starting point is a structured clinical evaluation, not a general estimate.
TMS therapy is available at Imindmental in Port St. Lucie, Vero Beach, and Stuart, FL
Imindmental offers TMS therapy for depression and anxiety at three Florida locations: Port St. Lucie, Vero Beach, and Stuart. The clinical team handles insurance verification before your first appointment, so you know your coverage status before committing to a course. Evaluations include a review of your treatment history, current medications, and protocol options so your planned session count and schedule are clear from day one.
For veterans and first responders, Imindmental provides tailored mental health treatment planning, including TMS, as part of a broader Florida mental health treatment approach. To schedule an evaluation or verify your insurance, contact the clinic directly through the TMS service page. The team can typically confirm availability and begin the pre-authorization process within the same week.
Sources
- Transcranial magnetic stimulation – Mayo Clinic
- Dosing transcranial magnetic stimulation in major depressive disorder: Relations between number of treatment sessions and effectiveness in a large patient registry
- TMS (Transcranial Magnetic Stimulation): What It Is – Cleveland Clinic
- Transcranial Magnetic Stimulation (TMS) – Treatment For Depression | VA Montana Health Care | Veterans Affairs
- Transcranial Magnetic Stimulation (TMS) – Brigham and Women’s Hospital
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.

